Volume: 16 Issue: 4 August 2018
FULL TEXT
Objectives: Kidney retransplant is increasingly performed, but patient survival is controversial. The aim of this study was to evaluate the outcomes of patients with second kidney grafts and compare survival rates of recipients with first and second kidney transplant procedures.
Materials and Methods: This was a retrospective study analyzing records from the Shiraz University of Medical Sciences transplant ward. Survival rates of retransplanted patients were compared with a randomly selected group of first kidney recipients. Factors related to retransplant survival were evaluated. Data were analyzed by SPSS version 16.0, and P < .05 was considered as significant.
Results: This study included 200 patients with first kidney transplants and 68 patients with kidney retransplants. We found that 1-, 3-, 5-, and 7-year graft survival rates were 91.9%, 87.2% ,86.3%, and 86.3% among retransplanted patients versus 98.3%, 95.4%, 90.2%, and 88.7% among the first transplant group (P = .130). Hospital stay duration after transplant, kidney rejection rate during hospitalization, delayed graft function, and creatinine levels at discharge were significantly associated with survival in retransplanted patients (P < .05).
Conclusions: Kidney retransplants can yield desirable outcomes and is the treatment of choice in patients who have lost their graft. Careful screening for risk factors should be consider for obtaining better results in second kidney transplant procedures.
Key words : Kidney grafts, Renal failure, Renal transplantation, Second kidney transplant
Introduction
Patients with failed kidney grafts need either dialysis or retransplant as renal replacement therapy.1-5 A patient receiving a kidney transplant can normally expect a benefit of more than 10 years. However, approximately 50% to 60% of recipients ultimately require retransplant because of chronic graft failure. Annually, 10% to 20% of all renal grafts are retransplant procedures with up to 20% of patients on wait lists for a repeat graft.1 In the United States, 15.3% of all kidney transplants are retransplants.2 Retransplant procedures, although technically more challenging in some patients, offer similar benefits in terms of quality of life and cost-effectiveness as the primary transplant. With improvements in surgical expertise and availability of more effective immunosuppressive drugs, many patients are being offered retransplants worldwide.2
Clinical follow-up confirms the significant continuing risks confronted by patients and their doctors after first transplant; however, data on risk factors and outcomes are scarce. Few studies have examined the relation between number of retransplants and graft outcomes.6-8 This information would be useful in deciding whether a patient with first allograft rejection should be considered for retransplant and, if so, what the likely outcome would be.
Therefore, the primary aim of this retrospective study was to evaluate the characteristics and outcomes of patients with second kidney allografts and related factors. Our secondary aim was to compare survival factors of recipients with first and second kidney transplants.
Materials and Methods
Setting and sampling
This was a retrospective study analyzing records from the Shiraz University of
Medical Sciences transplant ward. The first transplant group included 200 first
kidney recipients who were randomly selected from among 2175 patients seen at
the transplant ward in Namazi Hospital from March 1995 to March 2013. The second
group included all patients who had second transplants during this period. Based
on these criteria, 68 second transplant patients were included. The parameters
studied included patient and donor demographics (age and sex), donor type
(deceased or living), immunosuppressive drug regimen, primary cause of
end-stage renal disease, duration of dialysis before transplant, length of
hospital stay after transplant, and delayed graft function.
This study was approved by the ethics committee of Shiraz University of Medical Sciences, and all patients provided written informed consent regarding the use of their personal information. The study protocol was in accordance with the Declaration of Helsinki.
Statistical analyses
Data are presented as means and standard deviation for continuous variables and
as numbers and percentages for categorical variables. Graft survival rates in
the 2 groups were estimated using the Kaplan-Meier method and compared with the
log-rank test. Multivariate analysis was performed using Cox proportional hazard
model. Log-rank and chi-squared tests were used to determine the relation
between qualitative variables and survival. For data analyses, we used SPSS
software version 19 (SPSS, Chicago, IL, USA). P < .05 was considered as
statistically significant.
Results
Among 268 participants in this study, 200 patients (74.6%) were first kidney recipients and 68 patients (25.4%) were kidney retransplant recipients. The donor and recipient characteristics of the studied groups are presented in Table 1. The age of donors was significantly lower in the retransplant group (30.1 ± 10.4 vs 37.1 ± 12.8 years; P < .001). The first transplant group included 140 men (70.0%), with mean age at time of procedure of 56.0 ± 5.7 years and time on dialysis of 17.9 ± 14.1 months. The most prevalent underlying disease leading to kidney failure in the first transplant group was glomerulonephritis in 73 patients (36.5%). Most patients in this group received kidneys from living unrelated donors, in 82 patients (41.0%), versus deceased donors in 65 patients (32.5%). The mean length of hospital stay after transplant was 12.8 ± 5.8 days, with 55.0% of patients staying in the hospital for 2 weeks. Patients were treated with conventional immunosuppressive agents.
The retransplant group included 68 patients with mean age of 35.6 ± 12.2 years. The group included 46 men (67.6%), and known cause of renal failure was glomerulonephritis in 18 patients (26.5%). Patients in this group had mean dialysis duration before transplant of 13.8 ± 12.2 months. Most patients (33; 48.5%) received kidneys from deceased donors followed by living unrelated donors in 22 patients (33.8%). The mean length of hospital stay after transplant was 16.3 ± 9.4 days, with 54.4% of patients staying in the hospital for 2 weeks. Mean follow-up after hospitalization was 57.2 ± 5.3 months. In retransplant patients, 73.6% were negative for panel reactive antibody, and the remainder had panel reactive antibody lower than 20%. The median and mean of last serum creatinine level in patients with a functional graft was 1.3 ± 0.4 and 2.5 ± 2.3 mg/dL. Eighteen patients (26.5%) in the retransplant group had kidney rejection when they were still in hospital, with the most common cause being chronic kidney rejection (47 patients, 69.1%). As shown in Table 2, for most patients in this group, immunosuppression therapy for induction was intravenous injection of methylprednisolone (55 patients, 80.9%) and maintenance treatment was prednisolone, mycophenolate mofetil (CellCept, Roche Pharmaceuticals, Basel, Switzerland), and cyclosporine (52 patients, 76.5%).
Recipients were older in the first transplant group (P < .001). In addition, creatinine levels at time of discharge were higher in the retransplant group compared with the first transplant group (2.5 ± 2.4 vs 1.7 ± 1.2 mg/dL; P = .016). The mean length of hospital stays was higher in retransplanted patients (P = .006). Grafts were mostly from living unrelated donors in the transplant group and mostly from deceased donors in the retransplant group (P = .042).
Among our retransplant study group, 62 patients (91.0%) were alive, whereas 187 patients (93.5%) were alive at end of study in the first transplant group. As shown in Table 3 and Figure 1, when we compared patient survival between the 2 group, 1- to 7-year graft survival rates were higher in the first transplant patients; however, results were not significantly different from those who had second transplant (P = .130).
The relation between qualitative variables and survival in the retransplant patients was evaluated, with results shown in Table 4. Survival rates were slightly higher in female kidney recipients, although this was not significant (P = .605). The type of drug did not affect graft survival significantly, although survival rates were higher in patients who had methylprednisolone plus daclizumab (Zenapax; Roche, Pharmaceuticals, Basel, Switzerland) as induction therapy and the lowest in those who received prednisolone, mycophenolate mofetil, and cyclosporine as maintenance drugs (P > .05). Survival rates were higher in those who received living unrelated kidney donations, although this was not significant (P = .250). Both having delayed graft function and rejection in the hospital significantly affected graft survival, with significantly lower results in patients who had delayed graft function or rejection in the hospital (P < .001).
As shown in Table 5, survival rates were also significantly different according to hospitalization duration (hazard ratio of 1.06, 95% confidence interval, 1.01-1.1; P = 0.01) and creatinine levels at time of discharge (hazard ratio of 1.44, 95% confidence interval, 1.18-1.7; P < .001).
Discussion
Renal transplant improves life expectancy of patients with end-stage renal disease compared with patients who remain on dialysis. Transplant is also considered the optimal treatment for patients with first transplant failure by limited absolute contraindications.9-14 Although second transplant recipients show a wide range of risk factors (including high panel reactive antibody, surgical complications, and increased acute rejection episodes), the use of new immunosuppressive protocols has improved survival rates.8,12 The possibility of retransplant varies according to age, race, insurance, timing of graft loss, and peak panel reactive antibody.15 Therefore, retransplant needs careful risk factor monitoring.11
Patient survival after a second graft is controversial.3 As shown in previous studies,11,12,16 our present study documenting kidney retransplants at our transplant center shows that survival after retransplant is lower than after a first graft, although our results were not significant. Some studies have shown retransplant outcomes comparable to those after first transplant.13,17 Several studies have shown that the use of new immunosuppressive regimens and careful patient selection with high HLA matching result in survival with repeat grafts not significantly different from survival after first graft.12,13 In addition, no differences in acute rejection episodes, transplant complications, and serum creatinine levels have been shown by some investigations.8,18 Our retransplant group had higher creatinine levels at discharge and longer admission times compared with patients in the first transplant group.
Some previous studies have reported inferior graft survival rates after retransplant compared with primary transplant.2,8 A single center study showed that the second graft had more benefits of improved pretransplant screening and posttransplant management, and its survival rate was satisfactory and similar to that of the primary one.9 In addition, Arce and associates showed that survival after a second graft was significantly higher than after a first transplant and the number of complications was not increased.18 Improvements in survival after retransplant may be because of improved pretransplant screening, more sensitive crossmatching, better HLA matching, improved infectious disease prophylaxis, and more potent immunosuppressive regimens. Differences in retransplant outcomes could be explained by different criteria selection of candidates for a retransplant and the transplant organs.
Retransplant risk factors associated with survival have not been clearly defined.17 After we adjusted for some factors among our retransplant group, we found that patients with longer hospitalization, higher creatinine levels at discharge, delayed graft function, and greater graft rejection in hospital had poorer survival. Significant predictors of second graft loss in another study included donor age > 50 years, previous graft survival, time to retransplant, and delayed graft function after retransplant.17 Gjertson showed that lower age of recipients was correlated with poor graft function after retransplant.19
Survival rates after second graft in our patients were slightly higher in women, although not significantly, which is in accordance with the study by Gjertson.19 However, Pour-Reza-Gholi and associates reported that graft outcomes were slightly better in male retransplant patients.8
Survival rates of our patients were higher in those who received living unrelated donations, although not significantly. In another study, survival of patients receiving living related or unrelated donor retransplants showed > 5-year survival rates, but patients who received deceased donations showed poor long-term values.19 Similar to our study, Wang and associates showed that serum creatinine levels were significantly associated with survival of second graft.9 As in our study, Van Arendonk and associates showed that the primary cause of renal disease did not independently have a strong effect on the likelihood of retransplant.15
In the absence of randomization for patient selection among the 2 groups reported in our study, the possibility of confounding factors should be noticed.
Conclusions
This study showed that patient survival rates with retransplant were not significantly different from those after a first kidney graft. Because of the high prevalence of uremic patients and risk factors of end-stage renal disease in our center20-23 and to provide a better quality of life with the possibility of acceptable outcomes in retransplant, we should consider ways to achieve similar results of primary and secondary kidney transplants by careful screening for risk factors. Further investigations, especially multicenter studies, should be done to evaluate retransplant outcomes and risk factors before retransplant.
References:
- EBPG Expert Group on Renal Transplantation. European best practice
guidelines for renal transplantation. Section IV: Long-term management of
the transplant recipient. Nephrol Dial Transplant. 2002;17(Suppl 4):1-67.
CrossRef - PubMed - Magee JC, Barr ML, Basadonna GP, et al. Repeat organ transplantation in
the United States, 1996–2005. Am J Transplant. 2007;7(5 Pt 2):1424-1433.
CrossRef - PubMed - Marcén R, Pascual J, Tato AM, et al. Renal transplant recipient outcome
after losing the first graft. Transplant Proc. 2003;35(5):1679-1681.
CrossRef - PubMed - Ott U, Busch M, Steiner T, Schubert J, Wolf G. Renal retransplantation:
a retrospective monocentric study. Transplant Proc. 2008;40(5):1345-1348.
CrossRef - PubMed - Stratta RJ, Oh CS, Sollinger HW, Pirsch JD, Kalayoglu M, Belzer FO.
Kidney retransplantation in the cyclosporine era. Transplantation.
1988;45(1):40-45.
PubMed - Gutierrez R, Romero JA, Ricart JM, et al. Kidney retransplantation
prognostic factors in series of 84 cases. [in French]. J Urol.
1992;98(2):84-88.
PubMed - Ahmed K, Ahmad N, Khan MS, et al. Influence of number of retransplants
on renal graft outcome. Transplant Proc. 2008;40(5):1349-1352.
CrossRef - PubMed - Pour-Reza-Gholi F, Nafar M, Saeedinia A, et al. Kidney retransplantation
in comparison with first kidney transplantation. Transplant Proc.
2005;37(7):2962-2964.
CrossRef - PubMed - Wang D, Xu TZ, Chen JH, et al. Factors influencing second renal
allograft survival: a single center experience in China. Transpl Immunol.
2009;20(3):150-154.
CrossRef - PubMed - Dinis P, Nunes P, Marconi L, et al. Kidney retransplantation: Removal or
persistence of the previous failed allograft? Transplant Proc.
2014;46(6):1730-1734.
CrossRef - PubMed - Segoloni GP, Messina M, Basso E, Quercia A, Fop F. [Kidney
retransplantation: indications and limits.] G Ital Nefrol.
2009;26(2):191-200.
PubMed - Barocci S, Valente U, Fontana I, et al. Long-term outcome on kidney
retransplantation: a review of 100 cases from a single center. Transplant
Proc. 2009;41(4):1156-1158.
CrossRef - PubMed - Ingsathit A, Kantachuvesiri S, Rattanasiri S, et al. Long-term outcome
of kidney retransplantation in comparison with first kidney transplantation:
a report from the Thai Transplantation Registry. Transplant Proc.
2013;45(4):1427-1430.
CrossRef - PubMed - Rao PS, Schaubel DE, Wei G, Fenton SS. Evaluating the survival benefit
of kidney retransplantation. Transplantation. 2006;82(5):669-674.
CrossRef - PubMed - Van Arendonk KJ, Garonzik Wang JM, Deshpande NA, et al. Practice
patterns and outcomes in retransplantation among pediatric kidney transplant
recipients. Transplantation. 2013;95(11):1360-1368.
CrossRef - PubMed - Loupy A, Anglicheau D, Suberbielle C, et al. Long-term outcome of third
kidney transplants. Nephrol Dial Transplant. 2007;22(9):2693-2700.
CrossRef - PubMed - Arnol M, Prather JC, Mittalhenkle A, Barry JM, Norman DJ. Long-term
kidney regraft survival from deceased donors: risk factors and outcomes in a
single center. Transplantation. 2008;86(8):1084-1089.
CrossRef - PubMed - Arce J, Rosales A, Caffaratti J, et al. Renal retransplantation: risk
factors and results. Actas Urol Esp. 2011;35(1):44-50.
CrossRef - Gjertson DW. A multi-factor analysis of kidney regraft outcomes. Clin
Transpl. 2002:335-349.
PubMed - Khajehdehi P, Malekmakan L, Pakfetrat M, Roozbeh J, Sayadi M. Prevalence
of chronic kidney disease and its contributing risk factors in southern
Iran: a cross-sectional adult population-based study. Iran J Kidney Dis.
2014;8(2):109-115.
PubMed - Malekmakan L, Khajehdehi P, Pakfetrat M, Malekmakan A, Mahdaviazad H,
Roozbeh J. Prevalence of chronic kidney disease and its related risk factors
in elderly of southern Iran: a population-based study. ISRN Nephrol.
2013;2013:427230.
CrossRef - PubMed - Malekmakan L, Haghpanah S, Pakfetrat M, Malekmakan A, Khajehdehi P.
Causes of chronic renal failure among Iranian hemodialysis patients. Saudi J
Kidney Dis Transpl. 2009;20(3):501-504.
PubMed - Malekmakan L, Malekmakan A, Daneshian A, Pakfetrat M, Roosbeh J.
Hypertension and diabetes remain the main causes of chronic renal failure in
Fars Province, Iran 2013. Saudi J Kidney Dis Transpl. 2016;27(2):423-424.
CrossRef - PubMed

Volume : 16
Issue : 4
Pages : 386 - 390
DOI : 10.6002/ect.2016.0130
From the 1Department of Internal Medicine, the 2Department
of Community Medicine, Shiraz Nephro-Urology Research Center, and the 3Shiraz
Nephro-Urology Research Center, Shiraz University of Medical Sciences, Shiraz,
Iran
Acknowledgements: The Vice-Chancellery of Research and Technology of
Shiraz University of Medical Sciences financially supported this study, which
derived from a student’s thesis (Mehri Monavarian, No. 88-4791). The authors
declare that they have no conflicts of interest.
Corresponding author: Leila Malekmakan, Shiraz Nephro-Urology Research
Center, Shiraz University of Medical Sciences, Shiraz, Iran
Phone: +98 713 628 1563
E-mail: malekl@sums.ac.ir
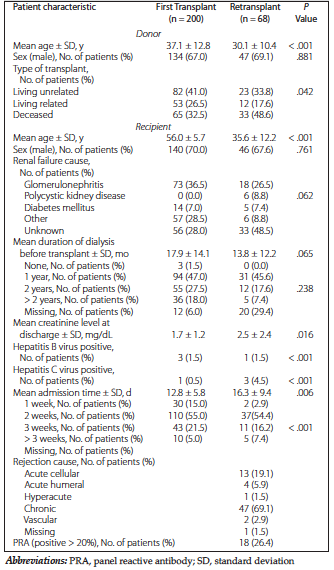
Table 1. Patient Characteristics in First and Second Transplant Study Groups
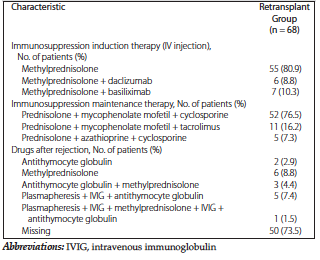
Table 2. Drug History in the Second Transplant Study Group Characteristic Retransplant
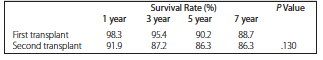
Table 3. Comparison of Survival in First Versus Second Transplant
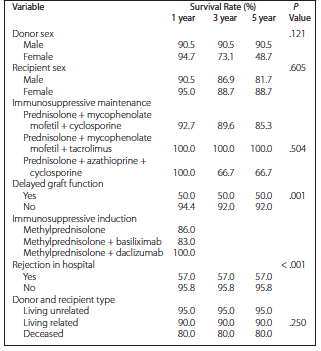
Table 4. Relation of Qualitative Variables and Survival in Kidney Retransplant Group
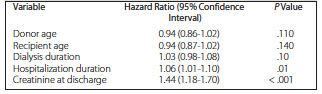
Table 5. Relation of Quantitative Variables and Survival in Kidney Retransplant Group
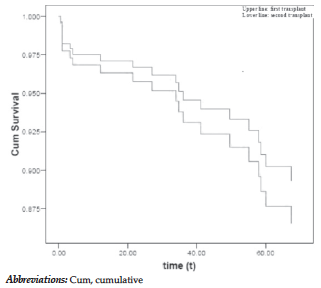
Figure 1. Graft Survival Rates in First Versus Second Transplant Patients