Volume: 12 Issue: 1 March 2014 - Supplement - 1
FULL TEXT
Objectives: Fibrin sealants may prevent hemorrhage and biliary leakage after liver resection. We evaluated the effects of topical fibrin glue application on biliary anastomosis in deceased-donor liver transplant.
Materials and Methods: From January 2011 to July 2013, fibrin glue was applied around the biliary anastomosis in 10 patients who had deceased-donor liver transplant (recipients: female, 8 patients; median age, 46.9 y) with end-to-end choledocho-choledochostomy in 9 patients and hepatico-jejunostomy in 1 patient. Biliary leakage was diagnosed with abdominal computed tomography.
Results: Biliary leakage was observed in 1 patient at 18 days after deceased-donor liver transplant with end-to-end choledochocholedochostomy. This was treated with revision laparotomy and reconstruction of the biliary anastomotic leak with a hepaticojejunostomy and placement of an internal stent and fibrin glue; the patient’s condition improved. There were no perioperative deaths.
Conclusions: In deceased-donor liver transplant, application of fibrin glue at the biliary anastomosis may be associated with a low frequency of postoperative biliary leak.
Key words : Bile duct, Complications, Hepatic failure, Surgery
Introduction
Biliary complications are common causes of morbidity after liver transplant and may require long-term and repeated therapies. The most common complications after deceased-donor liver transplant include biliary strictures (9% to 12% patients) and biliary leaks (5% to 10% patients).1 Biliary leak is a major cause of other complications such as wound infection, intra-abdominal abscess, and systemic sepsis. Risk factors for biliary complications after liver transplant include hepatic artery complications, advanced donor age, prolonged cold and warm ischemia times, grafts from donors after cardiac death, occurrence of a previous bile leak, T-tube use, cytomegalovirus infection, ABO incompatibility, and graft steatosis.1-3 However, there is controversy about technical aspects of biliary reconstruction, and factors that may contribute to biliary complications include inadequate surgical technique, small duct size, inappropriate suture material, and tension at the anastomosis.1,4
Nonrandomized and randomized studies have evaluated the association between fibrin glue application and gastrointestinal anastomotic leak after major visceral surgery.5-11 Randomized trials have not supported the benefits of fibrin glue that were reported from nonrandomized trials. Several studies about liver surgery have evaluated the efficacy of fibrin sealants on hemostasis, postoperative fluid drainage, and complications associated with the resection surface such as bile leakage, bleeding, and abscess formation.12 However, limited information is available about the application of fibrin glue to biliary anastomoses.13-15 A literature search showed no clinical studies or case series about the application of fibrin glue on biliary anastomoses in liver surgery or liver transplant.
We evaluated an adhesive fibrin glue sealant that consisted mainly of human fibrinogen and thrombin. The purpose of this study was to review the initial results of topical application of fibrin glue to biliary anastomoses during deceased-donor liver transplant.
Materials and Methods
Study design
From January 2011 to July 2013, there were 10 consecutive deceased-donor liver
transplants performed in 10 recipients at the Karadeniz Technical University
Farabi Hospital, a low-volume liver transplant service. Medical and procurement
records were collected prospectively. All transplants were evaluated regardless
of patient age, cause of liver failure, indication for transplant, or method of
biliary reconstruction, to evaluate the effects of many variables on biliary
complications. The study was approved by the Ethical Review Committee of the
institute. All protocols conformed with the ethical guidelines of the 1975
Helsinki Declaration. Informed consent was obtained from all subjects.
Surgery
All donors were deceased, but cardiac death donors were excluded. Donor organ
procurement was performed with retrograde aortic and inferior mesenteric venous
flush with University of Wisconsin preservative solution (4 to 5 L), packing in
the same solution, and a supraceliac aortic cross clamp. Blood and perfusate
were vented through the cavoatrial junction. The gallbladder and bile duct were
flushed on the back table in the operating room with a portal venous flush
(typically, 250 to 350 mL).
The procured organ was transplanted with an end-to-end choledochocholedochostomy (9 patients) without internal stenting or T-tube placement, and anastomoses were created with interrupted 5-0 or 6-0 absorbable polydioxanone sutures (Pedesente, Doğsan Cerrahi Dikiş Malzemeleri, Trabzon, Turkey). A Roux-en-Y hepaticojejunostomy was made at the discretion of the surgeon (primary surgery, 1 recipient; revision laparotomy, 1 patient) in patients who had common hepatic duct narrowing or primary sclerosing cholangitis, and anastomoses were created with interrupted 5-0 or 6-0 absorbable polydioxanone sutures, with or without internal stenting. In all recipients, bile duct reconstruction was performed by the same surgeon (ST) with surgical loupes (original magnification ×2.5). After completion of the biliary anastomosis, fibrin glue (Tisseel, Baxter Healthcare Corp., Glendale, CA, USA) was injected around the anastomosis. The abdominal cavity was drained with 3 Jackson-Pratt drains (right side of graft, left side of graft, and behind the hilum).
Aftercare
The immunosuppressive regimen included triple therapy with tacrolimus,
prednisone, and mycophenolate mofetil. Prednisone typically was stopped after
the first postoperative month but was continued in patients who had autoimmune
hepatitis, primary sclerosing cholangitis, or primary biliary cirrhosis after
deceased-donor liver transplant. Immunosuppression was decreased or minimized in
patients who had major infections or adverse events. Anticoagulant therapy
included acetylsalicylic acid (100 mg daily).
Doppler ultrasonography was performed daily during the first postoperative week. Suspected bile leak typically was evaluated with endoscopic retrograde cholangiopancreatography. Patients were classified as having an anastomotic bile leak when drain fluid to serum bilirubin ratio > 5, or when there was evidence of a leak on endoscopic retrograde cholangiopancreatography or percuta-neous transhepatic cholangiography. The Jackson-Pratt drains typically were removed at the end of the first postoperative week. When an abdominal fluid collection was suspected, computed tomography of the abdomen was performed to evaluate and guide percutaneous drainage of the collection. An anastomotic biliary stricture was defined as any obstructive lesion at the anastomosis detected postoperatively by cholangiography that required therapeutic intervention such as stent placement, cholangioplasty, or stent exchange. The drain fluid to serum bilirubin ratio, anastomotic leak, complications, and length of hospital stay were recorded.
Statistical analyses
Descriptive data were recorded. Categorical variables were expressed as number
(%), and continuous variables were expressed as median (range, minimum to
maximum). There were no intergroup comparisons or analyses performed because of
the small sample size.
Results
Most transplant recipients were female and had transplant because of hepatitis B virus infection (Table 1). Most donors were male, and 3 donors were extended criteria donors.16 There was no ABO incompatibility in any transplant. Most patients had an end-to-end choledochocholedochostomy (Table 2). Roux-en-Y hepaticojejunostomy without internal stent was performed because of an unsuitable common hepatic duct in a recipient who had congenital hepatic fibrosis.
Most complications were pulmonary (Table 3). Follow-up at median 18.2 months after surgery (range, 5-34 months) showed that all recipients had normal bilirubin level and graft function. There was 1 recipient who developed hepatorenal syndrome that was treated with chronic hemodialysis beginning 12 months after deceased-donor liver transplant (Table 3).
There was 1 patient who had an anastomotic leak; this 56-year-old woman recipient (MELD score, 24) had fulminant hepatic failure caused by methotrexate toxicity and had a deceased-donor liver transplant (donor, 13-year-old male) with end-to-end choledochocholedochostomy. Risk factors in this patient included grade 2 encephalopathy, bowel edema during vascular occlusion, and small duct size. All abdominal drains were removed at the end of first postoperative week. The drain fluid to serum bilirubin ratio was 2. A subcutaneous hematoma was drained 9 days after transplant, and a wound infection was diagnosed 13 days after transplant. The biliary leak was diagnosed with an abdominal computed tomography scan 18 days after transplant, and percutaneous drainage of the fluid collection was performed. An attempt to place an internal stent guided by endoscopic retrograde cholangiopancreatography was unsuccessful, and revision laparotomy was performed. There was no bowel edema evident. The biliary anastomotic leak was reconstructed with a hepaticojejunostomy and placement of an internal stent, and fibrin glue was placed around the revision anastomosis. The general condition of the patient improved, and she was discharged from the hospital 40 days after transplant.
Discussion
The present study showed anastomotic leak in only 1 of 10 patients who had fibrin glue as a supplement to biliary anastomoses that were created with interrupted 5-0 or 6-0 absorbable polydioxanone sutures. Biliary tract reconstruction is the final anastomotic step of deceased-donor liver transplant. In addition to risk factors for biliary complications in liver transplant, technical issues may cause biliary complications such as inadequate surgical technique, small duct size, inappropriate suture material, and tension at the anastomosis.1 End-to-end choledochocholedochostomy is rapid, simple, simulates the physiologic condition, and is used in 80% to 90% adult deceased-donor liver transplants.1,2,17-19 Hepaticojejunostomy is an alternative technique when end-to-end choledochocholedochostomy is not feasible because of anatomic reasons, hepatobiliary disease, or biliary complications that require surgical repair. End-to-end choledochocholedochostomy anastomoses typically are performed with interrupted or continuous monofilament absorbable sutures, and there is no difference in results between interrupted and continuous sutures.1,2,17-20
Most patients in the present study had an end-to-end choledochocholedochostomy anastomosis without an internal stent. Anastomotic stenting or use of a T-tube in biliary anastomosis in deceased-donor liver transplant is controversial. Many surgeons no longer use a T-tube in deceased-donor liver transplant. Recent studies have addressed the need for a T-tube including a systematic review, meta-analysis, and prospective randomized trial.21-23 A side-to-side choledochocholedochostomy is an alternative to end-to-end choledochocholedochostomy but is not commonly performed.24,25 Size discrepancy between recipient and donor bile ducts may be treated with a spatulated smaller duct or spatulation of the end-to-end choledochocholedochostomy with internal stenting.17,26 Increased anastomotic tension may occur in patients who have intestinal edema caused by total vascular exclusion during deceased-donor liver transplant. Inadequate collateral circulation is the main cause of intestinal edema during total vascular exclusion in patients who have fulminant liver failure without moderate or severe portal hypertension.
Fibrin sealants are topical hemostatic products that mimic the final stages of the blood coagulation process and are used commonly in liver surgery.12 Fibrin sealants contain thrombin and fibrinogen. When mixed together during the application of the sealant, thrombin cleaves fibrinogen to monomers that polymerize to form a fibrin gel.27,28 Several studies about fibrin sealants in liver surgery have shown reduced time to hemostasis when fibrin sealants are used, but few studies have evaluated bile leakage from the resection surface.12 Although different types of fibrin sealants have varied results, there is limited evidence that fibrin sealants reduce the incidence of bile leakage after liver resection.12 However, bile contains profibrinolytic activity that causes lysis of the clot formed by the fibrin sealant in vitro.29 Fibrin sealants may seal bile ducts and strengthen the common bile duct anastomosis, but experimental results are contradictory; fibrin sealants may prevent bile leakage from the anastomosis of the common bile duct in dogs but not pigs.13-15, 30 An alternative to fibrin sealants may be a synthetic sealant (polyethylene glycol-collagen biopolymer); in an experimental incomplete end-to-end choledochocholedochostomy after liver resection, the incidence of bile leakage was decreased by the synthetic sealant.31
In the present study, only 1 patient had a biliary leak that required radiologic intervention and reoperation. Risk factors for anastomotic leak in this patient included poor general condition, bowel edema during total vascular exclusion, and small duct size. The size discrepancy between donor and recipient common bile duct was resolved with hepaticojejunostomy and internal stent placement, with application of fibrin glue around the revision anastomosis. The risk factors in this patient were comparable to those in other patients who had biliary complications in large series of deceased-donor liver transplant.2,18 The frequency of extended criteria donors in the present study was comparable to other studies (Table 1).32 Despite comparable median cold ischemia time, the median warm ischemia time was longer in the present study than previous studies (Table 2). Information about donor cytomegalovirus status was unavailable, but all recipients were seropositive for cytomegalovirus immunoglobulin G and did not develop cytomegalovirus infection after deceased-donor liver transplant (Table 1). In the present study, the drain fluid to serum bilirubin ratio > 5 was not a useful marker for biliary anastomotic leak. Absence of anastomotic or nonanastomotic stricture in the present study was remarkable. Long-term follow-up of more patients is required for a more complete analysis of the present approach and the development of biliary strictures.
Limitations of the present study include the small sample size. Nevertheless, the present results support the use of fibrin glue application around the entire circumference of the biliary anastomosis in deceased-donor liver transplant. A larger prospective study may improve the reliability of these findings.
References:
- Gastaca M. Biliary complications after orthotopic liver transplantation:
a review of incidence and risk factors. Transplant Proc.
2012;44(6):1545-1549. doi: 10.1016/j.transproceed.2012.05.008.
CrossRef - PubMed - Sundaram V, Jones DT, Shah NH, et al. Posttransplant biliary
complications in the pre- and post-model for end-stage liver disease era.
Liver Transpl. 2011;17(4):428-435. doi: 10.1002/lt.22251.
CrossRef - PubMed - Dacha S, Barad A, Martin J, Levitsky J. Association of hepatic artery
stenosis and biliary strictures in liver transplant recipients. Liver
Transpl. 2011;17(7):849-854. doi: 10.1002/lt.22298.
CrossRef - PubMed - Koneru B, Sterling MJ, Bahramipour PF. Bile duct strictures after liver
transplantation: a changing landscape of the Achilles’ heel. Liver Transpl.
2006;12(5):702-704.
PubMed - Kram HB, Clark SR, Ocampo HP, Yamaguchi MA, Shoemaker WC. Fibrin glue
sealing of pancreatic injuries, resections, and anastomoses. Am J Surg.
1991;161(4):479-481; discussion 482.
CrossRef - PubMed - Suzuki Y, Kuroda Y, Morita A, et al. Fibrin glue sealing for the
prevention of pancreatic fistulas following distal pancreatectomy. Arch
Surg. 1995;130(9):952-955.
CrossRef - PubMed - Tashiro S, Murata E, Hiraoka T, Nakakuma K, Watanabe E, Miyauchi Y. New
technique for pancreaticojejunostomy using a biological adhesive. Br J Surg.
1987;74(5):392-394.
CrossRef - PubMed - Uemura K, Murakami Y, Hayashidani Y, et al. Combination of polyglicolic
acid felt and fibrin glue for prevention of pancreatic fistula following
pancreaticoduodenectomy. Hepatogastroenterology. 2009;56(94-95):1538-1541.
PubMed - Ochiai T, Sonoyama T, Soga K, et al. Application of polyethylene
glycolic acid felt with fibrin sealant to prevent postoperative pancreatic
fistula in pancreatic surgery. J Gastrointest Surg. 2010;14(5):884-890. doi:
10.1007/s11605-009-1149-3.
CrossRef - PubMed - Lillemoe KD, Cameron JL, Kim MP, et al. Does fibrin glue sealant
decrease the rate of pancreatic fistula after pancreaticoduodenectomy?
Results of a prospective randomized trial. J Gastrointest Surg.
2004;8(7):766-772; discussion 772-774.
CrossRef - PubMed - Upadhyaya VD, Gopal SC, Gangopadhyaya AN, et al. Role of fibrin glue as
a sealant to esophageal anastomosis in cases of congenital esophageal
atresia with tracheoesophageal fistula. World J Surg. 2007;31(12):2412-2415.
CrossRef - PubMed - de Boer MT, Boonstra EA, Lisman T, Porte RJ. Role of fibrin sealants in
liver surgery. Dig Surg. 2012;29(1):54-61. doi: 10.1159/000335735.
CrossRef - PubMed - Couto J, Kroczek B, Requena R, Lerner R. Autologous fibrin glue as a
sealant of the common bile duct. Surgery. 1987;101(3):354-356.
PubMed - Kram HB, Garces MA, Klein SR, Shoemaker WC. Common bile duct anastomosis
using fibrin glue. Arch Surg. 1985;120(11):1250-1256.
CrossRef - PubMed - Jones DB, Brewer JD, Meininger TA, Soper NJ. Sutured or fibrin-glued
laparoscopic choledochojejunostomy. Surg Endosc. 1995;9(9):1020-1027.
CrossRef - PubMed - Eurotransplant International Foundation. Eurotransplant Manual. Eurotransplant Web site. http://www.eurotransplant.org/cms/index.php?page=et_manual. Accessed December 31, 2013.
- Haberal M, Sevmis S, Karakayali H, Moray G, Torgay A, Arslan G. Bile
duct reconstruction without a stent in liver transplantation: early results
of a single center. Transplant Proc. 2008;40(1):240-244. doi:
10.1016/j.transproceed.2007.11.069.
CrossRef - PubMed - Welling TH, Heidt DG, Englesbe MJ, et al. Biliary complications
following liver transplantation in the model for end-stage liver disease
era: effect of donor, recipient, and technical factors. Liver Transpl.
2008;14(1):73-80.
CrossRef - PubMed - Akamatsu N, Sugawara Y, Hashimoto D. Biliary reconstruction, its
complications and management of biliary complications after adult liver
transplantation: a systematic review of the incidence, risk factors and
outcome. Transpl Int. 2011;24(4):379-392. doi:
10.1111/j.1432-2277.2010.01202.x.
CrossRef - PubMed - Castaldo ET, Pinson CW, Feurer ID, et al. Continuous versus interrupted
suture for end-to-end biliary anastomosis during liver transplantation gives
equal results. Liver Transpl. 2007;13(2):234-238.
CrossRef - PubMed - Sotiropoulos GC, Sgourakis G, Radtke A, et al. Orthotopic liver
transplantation: T-tube or not T-tube? Systematic review and meta-analysis
of results. Transplantation. 2009;87(11):1672-1680. doi:
10.1097/TP.0b013e3181a5cf3f.
CrossRef - PubMed - Riediger C, Müller MW, Michalski CW, et al. T-tube or no T-tube in the
reconstruction of the biliary tract during orthotopic liver transplantation:
systematic review and meta-analysis. Liver Transpl. 2010;16(6):705-717. doi:
10.1002/lt.22070.
CrossRef - PubMed - López-Andújar R, Montalvá E, Frangi A, et al. T-tube or not T-tube in deceased donor liver transplantation. Preliminary results of a prospective randomized trial [ILTS, ELITA, and LICAGE abstract O-79]. Liver Transpl. 2011;17(suppl 1):S103.
- Neuhaus P, Blumhardt G, Bechstein WO, Steffen R, Platz KP, Keck H.
Technique and results of biliary reconstruction using side-to-side
choledochocholedochostomy in 300 orthotopic liver transplants. Ann Surg.
1994;219(4):426-434.
CrossRef - PubMed - Davidson BR, Rai R, Kurzawinski TR, et al. Prospective randomized
trial of end-to-end versus side-to-side biliary reconstruction after
orthotopic liver transplantation. Br J Surg. 1999;86(4):447-452.
CrossRef - PubMed - Buczkowski AK, Schaeffer DF, Kim PT, et al. Spatulated end-to-end bile
duct reconstruction in orthotopic liver transplantation. Clin Transplant.
2007;21(1):7-12.
CrossRef - PubMed - Berrevoet F, de Hemptinne B. Use of topical hemostatic agents during
liver resection. Dig Surg. 2007;24(4):288-293.
CrossRef - PubMed - Mosesson MW. Fibrin polymerization and its regulatory role in
hemostasis. J Lab Clin Med. 1990;116(1):8-17.
PubMed - Boonstra EA, Adelmeijer J, Verkade HJ, de Boer MT, Porte RJ,
Lisman T. Fibrinolytic proteins in human bile accelerate lysis of plasma
clots and induce breakdown of fibrin sealants. Ann Surg.
2012;256(2):306-312. doi: 10.1097/SLA.0b013e31824f9e7e.
CrossRef - PubMed - Noun R, Elias D, Balladur P, et al. Fibrin glue effectiveness and
tolerance after elective liver resection: a randomized trial.
Hepatogastroenterology. 1996;43(7):221-224.
PubMed - Wise PE, Wudel LJ Jr, Belous AE, et al. Biliary reconstruction is
enhanced with a collagen-polyethylene glycol sealant. Am Surg.
2002;68(6):553-561; discussion 561-562.
PubMed - Goldaracena N, Quiñonez E, Méndez P, et al. Extremely marginal liver
grafts from deceased donors have outcome similar to ideal grafts. Transplant
Proc. 2012;44(7):2219-2222. doi: 10.1016/j.transproceed.2012.07.113.
CrossRef - PubMed

Volume : 12
Issue : 1
Pages : 76 - 80
DOI : 10.6002/ect.25Liver.O9
From the Department of Surgery, Karadeniz Technical University, School of
Medicine, Farabi Hospital, Trabzon, Turkey
Acknowledgements: The authors were surgeons who performed the liver transplants
(Serdar Topaloğlu and Adnan Çalık) or surgical residents who assisted in patient
care (Orhan Kalaycı, Kutay Sağlam, Ahmet Yazıcı, and Coşkun Aydın), and all
authors collected data for the study. The authors have no conflicts of interest
to disclose. No funding was received for this study.
Corresponding author: Serdar Topaloğlu, MD, Department of Surgery, Farabi
Hospital, 61080, Trabzon, Turkey
Phone: +90 505 477 2006
Fax: +90 462 325 0518
E-mail: serdartopaloglu@yahoo.com
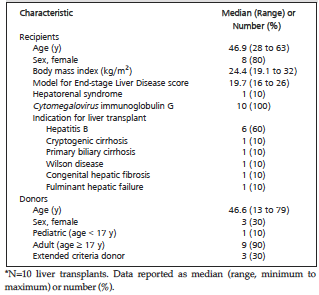
Table 1. Characteristics of Recipients and Donors of Liver Transplant*
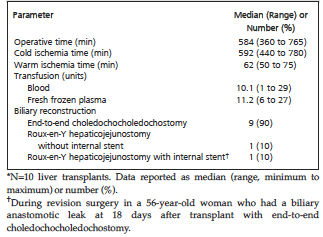
Table 2. Operative Parameters for Liver Transplant
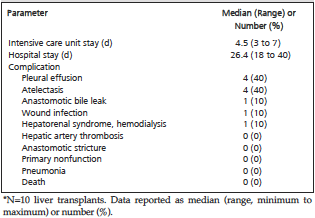
Table 3. Clinical Outcome After Liver Transplant*