Volume: 12 Issue: 1 March 2014 - Supplement - 1
FULL TEXT
Objectives: The Japanese Liver Transplantation Society is a cooperative research consortium, established in 1980 to characterize and follow trends in patient and graft survival in all liver transplants in Japan. This study evaluated the effect of graft size matching on survival in pediatric recipients of living-donor liver transplant
Materials and Methods: Between November 1989 and December 2010, there were 2224 patients aged < 18 years who received living-donor liver transplant in Japan. Survival was evaluated according to graft size matching.
Results: There were 998 male and 1226 female donors (median age, 35.2 y). There was no donor mortality associated with surgery. The median age of recipients was 4.0 years (range, 13 d to 17.9 y) and body weight was 16.6 kg (range, 2.6 to 90 kg). The survival of living-donor liver transplant recipients was greater for pediatric than adult recipients at 1 year (adult, 81%; pediatric, 88%), 5 years (adult, 72%; pediatric, 85%), 10 years (adult, 66%; pediatric, 83%), and 15 years (adult, 57%; pediatric, 80%) after transplant (difference between adult and pediatric recipients: P ≤ .0001). In the 2224 recipients aged < 18 years, the graft types included left lateral segment in 1549 recipients (70%), left lobe in 500 recipients (23%), reduced left lateral segment in 96 recipients (4%), right lobe in 76 recipients (3%), and posterior segment in 3 recipients (0.1%). There was no significant difference in survival between recipients that had different graft types. However, recipients aged < 1 year (296 recipients) who received grafts with graft-to-recipient body weight ratio > 4.0% had significantly worse patient survival because of problems associated with large-for-size grafts.
Conclusions: Living-donor liver transplant had greater survival in children than adult recipients. Graft-to-recipient body weight ratio was a significant prognostic factor in recipients aged < 1 year.
Key words : Children, Hepatic failure, Left lateral segment, Treatment
Introduction
Living-donor liver transplant was introduced in Japan in 1989 as a life-saving procedure in patients who have biliary atresia because of the scarcity of organs available for deceased-donor transplant.1 As a result of the restrictions imposed by the Deceased Organ Transplant Law of 1997, organs could not be obtained from deceased donors aged < 15 years. The law did not fully address the deceased-donor organ shortage, especially among pediatric patients in Japan. The organ transplant law was revised in June 2010, ending opposition to organ donation from deceased children aged < 15 years. However, there have been only 2 pediatric deceased-donor liver transplants since October 2012.
The shortage of deceased organ donors led to the development of unique technical, physiologic, and logistic innovations in living-donor liver transplant.2,3 Improvements in experience and techniques in living-donor surgery have increased the frequency of pediatric and adult living-donor liver transplant, with excellent patient and graft survival.4 With the improved techniques, the potential donor pool has increased and waiting list mortality has decreased for pediatric liver transplant.5 Candidates for living-donor liver transplant are limited strictly to relatives up to the third civil degree or spouses of the recipient who want to donate. The previous donor risk in Japan was acceptable (morbidity, 8.7%).6
There have been technical and immunologic refinements in the Japanese pediatric living-donor liver transplant program such as resolving graft size matching and overcoming blood type mismatch. The use of small-for-size grafts (graft-to-recipient body weight ratio < 0.8%) is associated with the development of small-for-size syndrome, massive ascites, renal insufficiency, persistent cholestasis, coagulopathy, infectious complications in patients with lower sized grafts, and reduced patient survival (especially in adolescents), most likely because of increased parenchymal cell injury and decreased metabolic and synthetic graft capacity.7 Large-for-size grafts are used in living-donor liver transplant in neonates and infants; the main problems associated with large-for-size grafts include the small size of the recipient’s abdominal cavity, size discrepancy between vascular lumens, and insufficient blood supply to the graft. Further reducing the size of the left lateral segment increases the possibility of supplying an adequate graft size, and a reduced or hyperreduced left lateral segment may mitigate the problems of large-for-size grafts with graft-to-recipient weight ratio > 4.0%.8
The Japanese Liver Transplantation Society is a cooperative research consortium that was established in 1980 to characterize and follow trends in patient and graft survival at all liver transplant centers in Japan. The purpose of the present study was to evaluate a large cohort of pediatric patients who had living-donor liver transplant.
Materials and Methods
Patients
We analyzed data for all living donors and recipients who had isolated living-donor
liver transplant and were enrolled in the Japanese Liver Transplantation Society
registry from November 1989 (inception of the registry) to December 2010. The
study patients were followed before living-donor liver transplant and annually
after transplant. The use of annual liver transplant registry data was approved
by the ethics committee of the Japanese Liver Transplantation Society.
Donor data obtained from the Japanese Liver Transplantation Society database included age, sex, blood type, relationship to the recipient, and graft type. The recipient data included age, sex, blood type, original liver disease, and outcome at the most recent follow-up (survival or death). During the study period, 6097 living-donor liver transplants were performed in Japan (minimum follow-up, 2 y), including 2224 children recipients (age < 18 y) (36%) and 3873 adult recipients (age ≥ 18 y) (64%). For the 2224 children recipients, there were 998 male and 1226 female living donors (median age, 35.2 y). The median age of pediatric recipients was 4.0 years (range, 13 d to 17.9 y) and body weight was 16.6 kg (range, 2.6 to 90 kg). During the previous 5 years, there were 130 to 140 pediatric living-donor liver transplants performed annually. During the same study period from 1989 to 2010, 96 deceased-donor liver transplants were performed in children, including 13 split liver transplants, and these patients were excluded from the present study. All recipients were followed until death, graft loss, or December 2010. The median follow-up was 10.6 years (range, 2.0 to 21.1 y).
Statistical analyses
Data analyses were performed with statistical software (IBM SPSS Statistics for
Windows, Version 19.0, IBM Corp., Armonk, NY, USA). Cumulative survival was
evaluated with Kaplan-Meier method, and differences in survival between groups
were evaluated with log-rank test. Factors associated with long-term patient
survival were analyzed with Cox proportional hazards regression model.
Statistical significance was defined by P ≤ .05.
Results
The survival of living-donor liver transplant recipients was greater for pediatric than adult recipients at 1 year (adult, 81%; pediatric, 88%), 5 years (adult, 72%; pediatric, 85%), 10 years (adult, 66%; pediatric, 83%), and 15 years (adult, 57%; pediatric, 80%) after transplant (difference between adult and pediatric recipients: P ≤ .0001) (Figure 1). In the initial transplants performed at Kyoto University (Kyoto, Japan) and the National Center for Child Health and Development (Tokyo, Japan), which were the pediatric transplant centers that had the highest number of transplants in Japan, recipients aged < 1 year (296 recipients) who received grafts with graft-to-recipient body weight ratio > 4.0% had significantly worse patient survival because of problems associated with large-for-size grafts (Figure 2). Reduced left lateral segment grafts were indicated for recipients who received grafts with an estimated graft-to-recipient body weight > 4.0% since September 2000 (Figure 3).8
In the 2224 recipients aged < 18 years, the graft types included left lateral segment in 1549 recipients (70%), left lobe in 500 recipients (23%), reduced left lateral segment in 96 recipients (4%), right lobe in 76 recipients (3%), and posterior segment in 3 recipients (0.1%). There was no significant difference in survival between recipients that had different graft types (Figure 4). There was no donor mortality associated with surgery in the 2224 pediatric living-donor liver transplants.
Discussion
In this large group of Japanese pediatric living-donor liver transplant recipients, frequency of survival was excellent (Figure 1). Liver graft size matching may be a major factor determining successful outcome in pediatric liver transplant. Graft-to-recipient body weight ratio was a significant prognostic factor in recipients aged < 1 year.
Liver transplants with reduced left lateral segment were started to address problems associated with large-for-size transplants. However, in very small children (body weight < 6 kg), the abdominal cavity may be small and the anteroposterior thickness of the graft could limit the potential for successful transplant because of the compartment syndrome. Reducing the left lateral segment thickness was introduced in neonatal living-donor liver transplant, but this did not improve recipient survival.9,10 Tailoring the graft size and reducing the thickness of the left lateral segment may enable safe transplant in small children without the associated complications of large-for-size grafts.
Approximately 20 years ago, the success of pediatric living-donor liver transplant using the left lateral segment led to the use of the same procedure in adolescent recipients.11 Occasional patient mortality caused by small-for-size grafts impeded the greater use of living-donor liver transplant in adolescents, and many centers began to use the right lobe from the donor to provide greater graft mass for the recipient to achieve better outcomes without compromising the living donor.12 In living-donor liver transplant, high morbidity in the donor of a right lobe graft has been reported, but successful living-donor liver transplant with a small-for-size graft may be anticipated with technical modifications such as the portal pressure modulation.13 In addition, increased use of deceased-donor liver transplant may minimize the need for living donors, especially for adolescent recipients. Increased experience and refinement of living-donor liver transplant may improve outcomes in pediatric patients having liver transplant.
References:
- Nagasue N, Kohno H, Matsuo S, et al. Segmental (partial) liver
transplantation from a living donor. Transplant Proc. 1992;24(5):1958-1959.
PubMed - Tanaka K, Uemoto S, Tokunaga Y, et al. Surgical techniques and innovations in
living related liver transplantation. Ann Surg. 1993:217(1):82-91.
CrossRef - PubMed - Makuuchi M, Kawasaki S, Noguchi T, et al. Donor hepatectomy for living
related partial liver transplantation. Surgery. 1993;113(4):395-402.
PubMed - Egawa H, Tanabe K, Fukushima N, Date H, Sugitani A, Haga H. Current status of
organ transplantation in Japan. Am J Transplant. 2012;12(3):523-530.
CrossRef - PubMed - de Ville de Goyet J, Hausleithner V, Reding R, Lerut J, Janssen M, Otte JB.
Impact of innovative techniques on the waiting list and result in pediatric
liver transplantation. Transplantation. 1993;56(5):1130-1136.
CrossRef - PubMed - Hashikura Y, Ichida T, Umeshita K, et al. Donor complications associated with
living donor liver transplantation in Japan. Transplantation.
2009;88(1):110-114.
CrossRef - PubMed - Kiuchi T, Kasahara M, Uryuhara K, et al. Impact of graft size mismatching on
graft prognosis in liver transplantation from living donors. Transplantation.
1999;67(2):321-327.
CrossRef - PubMed - Kasahara M, Fukuda A, Yokoyama S, et al. Living donor liver transplantation
with hyperreduced left lateral segments. J Pediatr Surg. 2008:43(8):1575-1578.
CrossRef - PubMed - Kasahara M, Sakamoto S, Shigeta T, et al. Reducing the thickness of left
lateral segment grafts in neonatal living donor liver transplantation. Liver
Transpl. 2013;19(2):226-228.
CrossRef - PubMed - Mizuta K, Yasuda Y, Egami S, et al. Living donor liver transplantation for
neonates using segment 2 monosubsegment graft. Am J Transplant.
2010;10(11):2547-2552.
CrossRef - PubMed - Hashikura Y, Makuuchi M, Kawasaki S, et al. Successful living-related
partial liver transplantation to an adult patient. Lancet.
1994;343(8907):1233-1234.
CrossRef - PubMed - Inomata Y, Uemoto S, Asonuma K, Egawa H. Right lobe graft in living donor
liver transplantation. Transplantation. 2000;69(2):258-264.
CrossRef - PubMed - Sainz-Barriga M, Scudeller L, Costa MG, de Hemptinne B, Troisi RI. Lack of a
correlation between portal vein flow and pressure: toward a shared
interpretation of hemodynamic stress governing inflow modulation in liver
transplantation. Liver Transpl. 2011;17(7):836-848.
CrossRef - PubMed

Volume : 12
Issue : 1
Pages : 1 - 4
DOI : 10.6002/ect.25Liver.L5
From the Japanese Liver Transplantation Society, Osaka, Japan
Acknowledgements: This work was supported in part by grants from the Scientific
Research Fund of the Ministry of Education (No. H24-4); a Research Grant for
Immunology, Allergy, and Organ Transplant from the Ministry of Health, Labour,
and Welfare (no. H25-8); and a grant from the Foundation for Growth Science,
Japan.
Corresponding author: Mureo Kasahara, MD, PhD, Transplantation Center, National
Center for Child Health and Development, 2-10-1 Okura, Setagaya-ku, Tokyo, Japan
157-8535
Phone: +81 3 3416 0181
Fax: +81 3 3416 2222
E-mail:
kasahara-m@ncchd.go.jp
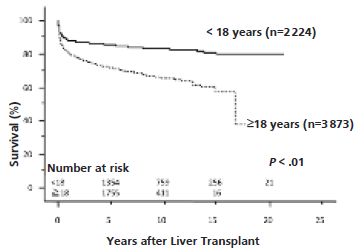
Figure 1. Survival of Pediatric and Adult Recipients After Living-donor Liver Transplant
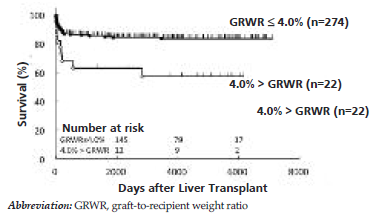
Figure 2. Relation Between Graft-to-recipient Body Weight Ratio and Survival of Living-donor Liver Transplant Recipients Aged < 1 Year (n=296)
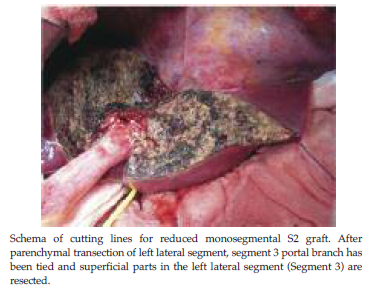
Figure 3. Monosegment Liver Transplant Graft (Segment 2)
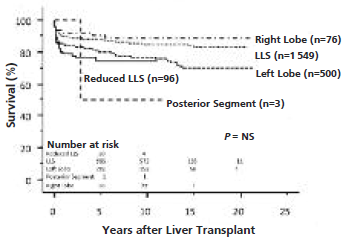
Figure 4. Relation Between Graft-to-recipient Body Weight Ratio and Survival of Living-donor Liver Transplant Recipients Aged < 1 Year (n=296)