Volume: 24 Issue: 8 August 2026
FULL TEXT
Early Persistent Proteinuria After Kidney Transplant as a Predictor of Long-Term Graft Outcomes: A Retrospective Cohort Study
Objectives: The source and clinical significance of early proteinuria following kidney transplantation are complex, as proteinuria may be transient or may derive from native kidneys. This study evaluated the effects of early persistent proteinuria on long-term kidney allograft outcomes.
Materials and Methods: We conducted a retrospective analysis of 312 kidney transplant recipients who received transplants between 2009 and 2020. Persistent proteinuria was defined as a spot urine protein-to-creatinine ratio ≥500 mg/g documented in at least 2 consecutive assessments within the first 24 months posttransplant. We compared graft survival according to proteinuria status.
Results: Among 312 study patients, proteinuria was detected in 46.3% of patients at a single visit and 16.0% met criteria for persistent proteinuria. Nineteen patients (6.1%) experienced graft loss. Single-visit proteinuria was associated with a 2-fold increased risk of graft loss, whereas persistent proteinuria demonstrated a stronger independent association (hazard ratio 4.68; 95% CI, 1.56-14.07; P = .006). Proteinuria documented at least twice at the 6-, 12-, and 24-month visits was related to an approximately 9-fold higher probability of graft loss (hazard ratio 8.63; 95% CI, 2.06-36.22; P = .003). Graft survival progressively declined with increasing levels of proteinuria.
Conclusions: Early persistent proteinuria is strongly and independently associated with adverse long-term graft outcomes. Frequent assessment of proteinuria can yield important prognostic insights and can help identify recipients who require enhanced monitoring and additional diagnostic evaluation.
Key words : Graft survival, Kidney function, Renal transplant
Introduction
Proteinuria is an important hallmark of kidney impairment and an essential parameter for the diagnosis and classification of chronic kidney disease (CKD).1 Damage to the glomerular filtration barrier, irrespective of etiology, leads to pathological proteinuria. Proteinuria also contributes to progressive kidney injury through podocyte dysfunction, epithelial-mesenchymal transition, glomerulosclerosis, and tubulointerstitial injury. These processes are mediated by mechanisms that include glomerular hypertension, mechanical stress, elevated angiotensin II activity, diminished vascular endothelial growth factor production, and upregulation of transforming growth factor-beta.2,3
Proteinuria serves as a risk factor for diminished kidney function, cardiovascular diseases, and patient mortality in both CKD patients and kidney transplant recipients (KTRs).4-8 In this context, proteinuria is used alongside estimated glomerular filtration rate (eGFR), protocol biopsies, and immunological markers such as anti-HLA donor-specific antibody (DSA) to identify potential allograft injury.9 The spot urine protein-to-creatinine ratio (UPCR) has been validated as a reliable alternative to 24-hour urine collection for estimating protein excretion in KTRs.10 According to the Kidney Disease: Improving Global Outcomes (KDIGO) clinical practice guidelines, UPCR should be assessed at least once throughout the first month posttransplant, every 3 months during the first year, and annually thereafter.11 However, the absence of clearly defined proteinuria thresholds in KTRs con-tributes to wide variability in reported prevalence, which has been shown to range between 7.5% and 45.0%.12
Proteinuria has demonstrated greater predictive power for transplant failure compared with anti-HLA DSA or histological markers in certain risk prediction models.13 Although donor-derived cell-free DNA has emerged as a potential indicator for antibody-mediated rejection, further validation is required before routine clinical implementation.14 Various studies have assessed the influence of pro-teinuria identified at specific posttransplant intervals, such as at 3 months, 6 months, or 1 year, on graft function. However, the prognostic significance of persistent proteinuria during the early posttransplant period remains insufficiently characterized.
This study aimed to address the effects of persis-tent proteinuria and the degree of proteinuria within the first 2 years after kidney transplant on long-term graft outcomes.
Materials and Methods
Study design and population
This single-center retrospective cohort study screened 540 patients who underwent kidney transplant from January 2009 to October 2020. Recipients under 18 years of age, those who were transplanted at other institutions, and those with follow-up periods shorter than 6 months were excluded. The final cohort comprised 457 KTRs. From these, 312 KTRs with complete proteinuria data were included in the final analysis.
We categorized patients based on posttransplant proteinuria status. The primary outcome was graft survival, defined as the time to graft loss, including return to dialysis, retransplant, or death with a functioning graft. We analyzed factors influencing proteinuria and graft survival.
The study was approved by the Ethical Review Committee of Ankara University (ID: İ3-230-21, March 29, 2021). All protocols conformed to the ethical guidelines of the 1975 Helsinki Declaration. Informed consent was waived due to the retros-pective study design.
Follow-up and data collection
We documented baseline demographic and clinical data, including recipient age, sex, primary kidney disease, comorbidities, dialysis vintage, HLA mis-match number, panel-reactive antibody status, donor characteristics, induction and maintenance immuno-suppressive therapies, posttransplant complications, and kidney function. We included posttransplant follow-up data for recipients at 1, 3, 6, 12, 18, and 24 months (Figure 1), as well as subsequent annual assessments. For laboratory parameters, we included serum creatinine, eGFR, tacrolimus trough level (TTL), and UPCR. Patients without graft loss were censored at their last clinical follow-up, and no patients were lost to follow-up during the study period.
All recipients received standard maintenance immunosuppressive therapy, consisting of tacrolimus, mycophenolic acid, and corticosteroids. Six patients received alternative regimens because of intolerance or clinical indications (1 received corticosteroids + azathioprine, 1 received corticosteroids + azathioprine + tacrolimus, 2 received corticosteroids + mycop-henolic acid, and 2 received corticosteroids + tacrolimus). Biopsy-proven acute rejection (BPAR) was diagnosed based on indication biopsies performed for progressive graft dysfunction or new-onset proteinuria ≥1000 mg/g and categorized according to the most recent Banff criteria.15
We recorded patient use of antiproteinuric medications, including angiotensin-converting en-zyme inhibitors (ACEi), angiotensin receptor blockers (ARB), diltiazem, spironolactone, and sodium-glucose cotransporter-2 inhibitors (SGLT2i).
Definition of proteinuria
Proteinuria was defined as UPCR ≥500 mg/g. Baseline recipient UPCR values were documented before transplant, and donor proteinuria data were unavailable. Persistent proteinuria was defined as UPCR ≥500 mg/g documented at 2 consecutive assessments within the first 2 posttransplant years. Recipients with proteinuria recorded at least twice at the 6-, 12-, and 24-month visits were analyzed separately. Proteinuria burden was further categorized as <500 mg/g, 500 to 999 mg/g, 1000 to 2999 mg/g, and ≥3000 mg/g.
Statistical analyses
We used SPSS software (version 25) for statistical evaluation. We presented continuous data as mean ± SD for normally distributed variables or as median (interquartile range [IQR]) for nonnormally distributed variables. We presented categorical data as counts and percentages. We performed between-group com-parisons using the t test or the Mann-Whitney U test for continuous variables and the χ2 or Fisher exact for categorical variables. We assessed allograft survival using Kaplan-Meier analysis. We included variables significant in univariable log-rank analysis (P < .05) and fulfilling proportional hazards assumptions in Cox proportional hazards regression models and calculated hazard ratios (HRs) and 95% CIs. Model selection also considered clinical relevance and collinearity to minimize overfitting. We evaluated proportional hazards assumptions and model adequacy using residual-based diagnostics. Statistical significance was defined as P < .05.
Results
Baseline and clinical features
Among 457 KTRs, 212 (46.3%) exhibited proteinuria at least once during follow-up. Of the 312 patients with complete proteinuria data from all 6 follow-up visits, 50 (16.0%) met criteria for persistent proteinuria, whereas 262 (84.0%) did not. Thirty-two patients (12.2%) had proteinuria documented at least twice at the 6-, 12-, and 24-month visits. Median UPCR values at these time points were 730 mg/g (IQR, 7033), 720 mg/g (IQR, 5780), and 710 mg/g (IQR, 11 190), respectively. Table 1 lists the demographic and clinical characteristics of the 312 patients stratified by per-sistent proteinuria status. Median recipient age was 41 years (IQR, 12), with a greater percentage of male (60.6%) than female patients. Chronic glome-rulonephritis was the most common etiology of CKD (28.5%), followed by diabetes (11.9%). Among included KTRs, 21% received kidneys from deceased donors. All living donors were related adults aged ≥18 years, predominantly parents (35.7%) and spouses (19.5%).
No significant differences were observed in maintenance immunosuppressive regimens between groups. Most KTRs received the same standard regimen consisting of tacrolimus, mycophenolic acid, and corticosteroids (96.0% in the persistent proteinuria group vs 98.5% in those without persistent proteinuria; P = .247). At 12 months, TTL values were comparable between groups (6.4 vs 6.0 ng/mL; P = .230), suggesting calcineurin inhibitor exposure was unlikely to account for persistent proteinuria.
Biopsy-proven acute rejection developed in 61 KTRs (19.5%), and rejection episodes were classified as borderline (n = 11, 18.0%), T-cell-mediated rejection (n = 30, 49.2%), antibody-mediated rejection (n = 17, 27.9%), and mixed-type rejection (n = 3, 4.9%). Among KTRs, 25% received ACEi or ARB. Two patients were administered diltiazem, 2 were prescribed spiro-nolactone, and 1 was treated with an SGLT2i.
Comparison according to proteinuria status
In KTRs with persistent proteinuria compared with those without persistent proteinuria, dialysis vintage was significantly longer (9.0 years vs 0.3 years; P < .001) and deceased donor transplant was more frequent (48.0% vs 16.4%; P < .001). Immunological factors, including HLA mismatch number and panel reactive antibody positivity, were similar between groups (P = .41 and P = .25). However, BPAR was more prevalent in the persistent proteinuria group than in those without persistent proteinuria (32.0% vs 17.2%; P = .015). BK virus infection (36.0% vs 19.5%; P = .010) and cytomegalovirus (CMV) viremia (20.0% vs 9.2%; P = .024) were also more common in the persistent proteinuria group (Table 2). During 5-year follow-up, kidney function deterioration was more pronounced in KTRs with persistent proteinuria, who also demonstrated a significantly higher inci-dence of graft loss (20% vs 3.4%; P = .038).
Analysis of graft survival
Among 312 KTRs, 19 (6.1%) experienced graft loss. Causes of graft loss included chronic rejection (n = 9, 47.4%), BPAR (n = 4, 21.1%), infection (n = 3, 15.8%), death with a functioning graft (n = 2, 10.5%), and recurrent/de novo glomerulonephritis (n = 1, 5.3%).
In univariable analysis, longer dialysis vintage (HR 1.07; 95% CI, 1.02-1.11; P = .004), deceased donor transplant (HR 2.39; 95% CI, 1.30-4.40; P = .005), BPAR (HR 2.61; 95% CI, 1.46-4.69; P = .001), CMV viremia (HR 2.14; 95% CI, 1.14-4.03; P = .019), and elevated serum creatinine levels at month 6 (HR 1.64; 95% CI, 1.32-2.03; P < .001) were significantly asso-ciated with graft loss (Table 3). Tacrolimus admi-nistration and higher TTL values showed reduced probability of graft loss. Proteinuria ≥500 mg/g at 3, 6, and 12 months was associated with a 1.5-, 3-, and 2-fold increased risk of graft loss, respectively. Persistent proteinuria was associated with an approximately 8-fold increased risk of graft loss (HR 7.65; 95% CI, 3.01-19.45; P < .001). Proteinuria docu-mented at least twice at the 6-, 12-, and 24-month visits was associated with an even higher risk of graft loss (HR 14.83; 95% CI, 4.32-50.97; P < .001).
In multivariable analysis, single-visit proteinuria remained associated with a 2-fold increased risk of graft loss (HR 2.30; 95% CI, 1.04-5.07; P = .039). Persistent proteinuria demonstrated a stronger inde-pendent association (HR 4.68; 95% CI, 1.56-14.07; P = .006) (Table 4, Figure 2A). The probability of graft loss was approximately 9 times higher in individuals exhibiting proteinuria at least twice at 6, 12, and 24 months (HR 8.63; 95% CI, 2.06-36.22; P = .003) (Figure 2B). In addition, higher TTL values at month 12 were independently associated with a reduced risk of graft loss (HR 0.56; 95% CI, 0.34-0.93; P = .003). Kaplan-Meier analyses demonstrated progressively worse graft survival with increasing proteinuria burden at 6, 12, and 24 months (Figure 3).
Discussion
Our study uniquely highlighted that persistent proteinuria within the first 2 years after kidney transplant was strongly and independently associated with inferior long-term graft survival. Furthermore, a higher burden of proteinuria demonstrated a graded association with negative outcomes.
The reported prevalence of posttransplant pro-teinuria varies widely due to discrepancies in sample sizes and the proteinuria thresholds. In KTRs, the prevalence of proteinuria over 0.15 g/day has been reported to range from 45% to 82%.16,17 When a cutoff of >0.5 g/day has been applied, prevalence rates were shown to range from 13.2% to 36.4%.7,8,18-20 In our cohort, 46.4% of KTRs exhibited proteinuria ≥0.5 g/day at least once within the first 2 years; however, only 16% met criteria for persistent proteinuria. Consistent with previous reports that demonstrated rapid resolution of native kidney-derived proteinuria after transplant,21 proteinuria present before transplant rarely (5.3%) persisted beyond the first year posttransplant in preemptively transplanted recipients.
Persistent or newly developed proteinuria post-transplant, along with increased levels of proteinuria, frequently reflects underlying allograft glomerular pathology.4,16,21 Previous biopsy-based studies have identified recurrent or de novo glomerulonephritis,4,18 transplant glomerulopathy,4,16,22,23 microvascular inflammation,4 and BPAR8,24 as common etiologies. Advanced donor age, prior transplant history, underlying kidney diseases such as glomerulonep-hritis or diabetes, hepatitis C infection, hypertension, body mass index >25 kg/m2, delayed graft function, urinary tract infections, viral infections, use of the mammalian target of rapamycin inhibitors, HLA incompatibility, and anti-HLA antibodies have been identified as additional contributors of proteinuria.4,8,16,20,23-26 In our cohort, deceased donor transplant, longer dialysis vintage, and dialysis history were identified as risk factors for persistent proteinuria. The increased incidence of BPAR and viral infections (BK and CMV) in this group further supported the association between proteinuria and both immunologic and structural injury. Considering that urinary tract infection is a transient cause of proteinuria, we did not identify urinary tract infection as a determining factor for persistent proteinuria.
Irrespective of the etiology, posttransplant pro-teinuria has been strongly associated with poor long-term graft prognosis. Even low-grade proteinuria (150-500 mg/day) has been demonstrated to confer increased risk, with a gradual correlation between protein excretion and graft loss.7,16,17,27,28 The Spanish Chronic Allograft Nephropathy Study, comprising 3365 transplant recipients, revealed that proteinuria of 0.5 to 1 g/day in the first year posttransplant elevated the probability of graft loss by 2.5 times, whereas proteinuria exceeding 1 g/day raised this risk by 3.5 times.8 A study that assessed 24-hour urine protein and kidney allograft biopsy in 738 KTRs established that proteinuria over 1 g/day, instead of proteinuria below 1 g/day, was inde-pendently indicative of graft loss, irrespective of eGFR and allograft histology.4 The incidence of death-censored graft loss escalated with elevated albuminuria across all eGFR levels.29 Applying lower proteinuria cutoffs may classify a larger proportion of recipients as proteinuria, increasing heterogeneity and diluting risk discrimination related to clinically meaningful proteinuria. Accordingly, the ≥500 mg/g threshold represents a pragmatic balance between clinical relevance and risk stratification, consistent with prior large cohort studies.8,16 In our study, persistent proteinuria was associated with an approximately 5-fold higher risk of graft loss, whereas repeated documentation of proteinuria at least twice at 6, 12, and 24 months conferred nearly a 9-fold increase. These findings emphasize the prognostic value of repeated proteinuria assessment rather than reliance on a single assessment, parti-cularly in high-risk individuals. Recent evidence consistently indicated that the detrimental effect of low-grade proteinuria on graft survival is intensified in recipients with de novo anti-HLA DSA and advancing donor age.30,31
Early posttransplant proteinuria likely reflects multiple intersecting mechanisms, including podocyte injury, subclinical rejection, endothelial dysfunction, calcineurin inhibitor-related toxicity, ischemia-reper-fusion injury, hyperfiltration, recurrent or de novo glomerular disease, and viral infections.32-36 Filtered proteins may further amplify tubular inflammation and fibrosis, contributing to chronic allograft damage. Thus, persistent proteinuria should be interpreted not as an isolated laboratory abnormality but as a surrogate marker of ongoing structural or immunologic stress on the allograft.
From a clinical perspective, these findings highlight the importance of management of KTRs with per-sistent proteinuria. Although current KDIGO guide-lines recommend biopsy for unexplained proteinuria >3 g/day,11 accumulating evidence, including our data, suggests that lower thresholds (500-1000 mg/day) may warrant earlier investigation. In addition to etiology specific, general nephro-protective measures, including blood pressure control, lipid management, reduced salt intake, maintenance of optimal body weight, and smoking cessation, should be optimized. Although renin-angiotensin system blockade may reduce proteinuria,37-39 its impact on long-term graft survival remains uncertain.40-43 Emerging data have suggested potential benefits of SGLT2i in diabetic KTRs,44-48 but broader application requires further investigation.49
The primary strength of our study is its assessment of the effects of persistent proteinuria on graft survival, along with the uniform implementation of a standard triple immunosuppressive regimen across all patients. Our study had several limitations. The single-center, retrospective design was susceptible to selection and information bias. The absence of protocol biopsies and routine DSA assessment limited etiological interpretation. Therefore, proteinuria in our cohort should be interpreted as a nonspecific surrogate marker of allograft injury rather than a patho-physiologically defined endpoint. The relatively small number of graft loss events (n = 19) may limit statistical power and increase the risk of model overfitting. Consequently, the independent effects of certain predictors should be interpreted with caution. The use of ACEi or ARB for various indications and the limited prescription of alternative antiproteinuric agents restricted the evaluation of the effects of these medications on graft survival. In addition, we utilized UPCR as an alternative to the 24-hour urine evaluation, which is considered the gold standard for assessment of proteinuria. It is important to note that a significant correlation has been demonstrated between UPCR and 24-hour urine protein in KTRs, with both sensitivity and specificity exceeding 80%.50
Conclusions
In this retrospective cohort study, early persistent proteinuria is a robust and independent predictor of adverse long-term graft outcomes. Routine longitu-dinal assessment of proteinuria may improve risk stratification and help identify KTRs who require intensified monitoring and targeted evaluation.
References:
- Kidney Disease: Improving Global Outcomes (KDIGO) CKD Work Group. KDIGO 2024 clinical practice guideline for the evaluation and management of chronic kidney disease. Kidney Int. 2024;105(4):S117-S314. doi:10.1016/j.kint.2023.10.018
CrossRef - PubMed - Longhitano E, Calabrese V, Casuscelli C, et al. Proteinuria and progression of renal damage: the main pathogenetic mechanisms and pharmacological approach. Medicina (Lithuania). 2024;60(11):1821. doi:10.3390/medicina60111821
CrossRef - PubMed - Toblli JE, Bevione P, Di Gennaro F, Madalena L, Cao G, Angerosa M. Understanding the mechanisms of proteinuria: therapeutic implications. Int J Nephrol. 2012;2012:546039. doi:10.1155/2012/546039
CrossRef - PubMed - Naesens M, Lerut E, Emonds MP, et al. Proteinuria as a noninvasive marker for renal allograft histology and failure: an observational cohort study. J Am Soc Nephrol. 2016;27(1):281-292. doi:10.1681/ASN.2015010062
CrossRef - PubMed - Roodnat JI, Mulder PG, Rischen-Vos J, et al. Proteinuria after renal transplantation affects not only graft survival but also patient survival. Transplantation. 2001;72(3):438-444. doi:10.1097/00007890-200108150-00014
CrossRef - PubMed - Weiner DE, Park M, Tighiouart H, et al. Albuminuria and allograft failure, cardiovascular disease events, and all-cause death in stable kidney transplant recipients: a cohort analysis of the FAVORIT trial. Am J Kidney Dis. 2019;73(1):51-61. doi:10.1053/j.ajkd.2018.05.015
CrossRef - PubMed - Halimi JM, Buchler M, Al-Najjar A, et al. Urinary albumin excretion and the risk of graft loss and death in proteinuric and non-proteinuric renal transplant recipients. Am J Transplant. 2007;7(3):618-625. doi:10.1111/j.1600-6143.2007.01665.x
CrossRef - PubMed - Fernández-Fresnedo G, Plaza JJ, Sánchez-Plumed J, Sanz-Guajardo A, Palomar-Fontanet R, Arias M. Proteinuria: a new marker of long-term graft and patient survival in kidney transplantation. Nephrol Dial Transplant. 2004;19(Suppl 3):iii47-51. doi:10.1093/ndt/gfh1015
CrossRef - PubMed - Josephson MA, Becker Y, Budde K, et al. Challenges in the management of the kidney allograft: from decline to failure: conclusions from a Kidney Disease: Improving Global Outcomes (KDIGO) Controversies Conference. Kidney Int. 2023;104(6):1076-1091. doi:10.1016/j.kint.2023.05.010
CrossRef - PubMed - Mrevlje M, Oblak M, Mlinšek G, Lindić J, Jadranka-Buturović-Ponikvar, Arnol M. First and second morning spot urine protein measurements for the assessment of proteinuria: a diagnostic accuracy study in kidney transplant recipients. BMC Nephrol. 2021;22(1):192. doi:10.1186/s12882-021-02406-x
CrossRef - PubMed - Kasiske BL, Zeier MG, Chapman JR, et al. KDIGO clinical practice guideline for the care of kidney transplant recipients: a summary. Kidney Int. 2010;77(4):299-311. doi:10.1038/ki.2009.377
CrossRef - PubMed - Shamseddin MK, Knoll GA. Posttransplantation proteinuria: an approach to diagnosis and management. Clin J Am Soc Nephrol. 2011;6(7):1786-1793. doi:10.2215/CJN.01310211
CrossRef - PubMed - Loupy A, Aubert O, Orandi BJ, et al. Prediction system for risk of allograft loss in patients receiving kidney transplants: international derivation and validation study. BMJ. 2019;366:14923. doi:10.1136/bmj.l4923
CrossRef - PubMed - Xiao H, Gao F, Pang Q, et al. Diagnostic accuracy of donor-derived cell-free DNA in renal-allograft rejection: a meta-analysis. Transplantation. 2021;105(6):1303-1310. doi:10.1097/TP.0000000000003443
CrossRef - PubMed - Loupy A, Haas M, Roufosse C, et al. The Banff 2019 Kidney Meeting Report (I): updates on and clarification of criteria for T cell- and antibody-mediated rejection. Am J Transplant. 2020;20(9):2318-2331. doi:10.1111/ajt.15898
CrossRef - PubMed - Amer H, Fidler ME, Myslak M, et al. Proteinuria after kidney transplantation, relationship to allograft histology and survival. Am J Transplant. 2007;7(12):2748-2756. doi:10.1111/j.1600-6143.2007.02006.x
CrossRef - PubMed - Cherukuri A, Welberry-Smith MP, Tattersall JE, et al. The clinical significance of early proteinuria after renal transplantation. Transplantation. 2010;89(2):200-207. doi:10.1097/TP.0b013e3181c352c5
CrossRef - PubMed - Chung J, Park S, Park J, Kim SC, Han DJ, Yu E. Glomerulonephritis is the major cause of proteinuria in renal transplant recipients: histopathologic findings of renal allografts with proteinuria. Clin Transplant. 2000;14(5):499-504. doi:10.1034/j.1399-0012.2000.140509.x
CrossRef - PubMed - Fernandez-Fresnedo G, Escallada R, Rodrigo E, et al. The risk of cardiovascular disease associated with proteinuria in renal transplant patients. Transplantation. 2002;73(8):1345-1348. doi:10.1097/00007890-200204270-00028
CrossRef - PubMed - Sancho A, Gavela E, Ávila A, et al. Risk factors and prognosis for proteinuria in renal transplant recipients. Transplant Proc. 2007;39(7):2145-2147. doi:10.1016/j.transproceed.2007.07.005
CrossRef - PubMed - Myslak M, Amer H, Morales P, et al. Interpreting post-transplant proteinuria in patients with proteinuria pre-transplant. Am J Transplant. 2006;6(7):1660-1665. doi:10.1111/j.1600-6143.2006.01361.x
CrossRef - PubMed - Li X, Chen J, Cheng D, et al. Histopathologic features that predict transplant glomerulopathy progression in a Chinese cohort. Am J Nephrol. 2019;49(6):425-434. doi:10.1159/000500043
CrossRef - PubMed - Zhang Q, Budde K, Schmidt D, et al. Clinicopathologic features and risk factors of proteinuria in transplant glomerulopathy. Front Med (Lausanne). 2021;8:666319. doi:10.3389/fmed.2021.666319
CrossRef - PubMed - Oblak M, Mlinšek G, Kojc N, Frelih M, Buturović-Ponikvar J, Arnol M. Spot urine protein excretion in the first year following kidney transplantation associates with allograft rejection phenotype at 1-year surveillance biopsies: an observational national-cohort study. Front Med (Lausanne). 2021;8:781195. doi:10.3389/fmed.2021.781195
CrossRef - PubMed - Budde K, Lehner F, Sommerer C, et al. Five-year outcomes in kidney transplant patients converted from cyclosporine to everolimus: the randomized ZEUS study. Am J Transplant. 2015;15(1):119-128. doi:10.1111/ajt.12952
CrossRef - PubMed - Armstrong KA, Campbell SB, Hawley CM, Nicol DL, Johnson DW, Isbel NM. Obesity is associated with worsening cardiovascular risk factor profiles and proteinuria progression in renal transplant recipients. Am J Transplant. 2005;5(11):2710-2718. doi:10.1111/j.1600-6143.2005.01073.x
CrossRef - PubMed - Kang NR, Lee JE, Huh W, et al. Minimal proteinuria one year after transplant is a risk factor for graft survival in kidney transplantation. J Korean Med Sci. 2009;24(SUPPL.1):S129-S134. doi:10.3346/jkms.2009.24.S1.S129
CrossRef - PubMed - Sancho Calabuig A, Pallardó Mateu LM, Avila Bernabeu AI, Gavela Martínez E, Beltrán Catalán S, Crespo Albiach JF. Very low-grade proteinuria at 3 months posttransplantation is an earlier marker of graft survival. Transplant Proc. 2009;41(6):2122-2125. doi:10.1016/j.transproceed.2009.06.137
CrossRef - PubMed - Lam NN, Tonelli M, Lentine KL, et al. Albuminuria and posttransplant chronic kidney disease stage predict transplant outcomes. Kidney Int. 2017;92(2):470-478. doi:10.1016/j.kint.2017.01.028
CrossRef - PubMed - López Del Moral C, Wu K, Naik M, et al. Predictors of graft failure after first detection of de novo donor-specific HLA antibodies in kidney transplant recipients. Nephrol Dial Transplant. 2024;39(1):84-94. doi:10.1093/ndt/gfad149
CrossRef - PubMed - Diena D, Messina M, De Biase C, et al. Relationship between early proteinuria and long term outcome of kidney transplanted patients from different decades of donor age. BMC Nephrol. 2019;20(1):443. doi:10.1186/s12882-019-1635-0
CrossRef - PubMed - Jiang H, Shen Z, Zhuang J, et al. Understanding the podocyte immune responses in proteinuric kidney diseases: from pathogenesis to therapy. Front Immunol. 2023;14:1335936. doi:10.3389/fimmu.2023.1335936
CrossRef - PubMed - Riella L V., Djamali A, Pascual J. Chronic allograft injury: mechanisms and potential treatment targets. Transplant Rev. 2017;31(1):1-9. doi:10.1016/j.trre.2016.10.005
CrossRef - PubMed - Hošková L, Málek I, Kopkan L, Kautzner J. Pathophysiological mechanisms of calcineurin inhibitor-induced nephrotoxicity and arterial hypertension. Physiol Res. 2017;66(2):167-180. doi:10.33549/physiolres.933332
CrossRef - PubMed - Ponticelli C, Graziani G. Proteinuria after kidney transplantation. Transpl Int. 2012;25(9):909-917. doi:10.1111/j.1432-2277.2012.01500.x
CrossRef - PubMed - Naik AS, Afshinnia F, Aqeel J, et al. Accelerated podocyte detachment early after kidney transplantation is related to long-term allograft loss of function. Nephrol Dial Transplant. 2019;34(7):1232-1239. doi:10.1093/ndt/gfy350
CrossRef - PubMed - Philipp T, Martinez F, Geiger H, et al. Candesartan improves blood pressure control and reduces proteinuria in renal transplant recipients: results from SECRET. Nephrol Dial Transplant. 2010;25(3):967-976. doi:10.1093/ndt/gfp581
CrossRef - PubMed - Mandelbrot DA, Alberú J, Barama A, et al. Effect of ramipril on urinary protein excretion in maintenance renal transplant patients converted to sirolimus. Am J Transplant. 2015;15(12):3174-3184. doi:10.1111/ajt.13384
CrossRef - PubMed - Hiremath S, Fergusson D, Doucette S, Mulay A V., Knoll GA. Renin angiotensin system blockade in kidney transplantation: a systematic review of the evidence. Am J Transplant. 2007;7(10):2350-2360. doi:10.1111/j.1600-6143.2007.01928.x
CrossRef - PubMed - Knoll GA, Fergusson D, Chassé M, et al. Ramipril versus placebo in kidney transplant patients with proteinuria: a multicentre, double-blind, randomised controlled trial. Lancet Diabetes Endocrinol. 2016;4(4):318-326. doi:10.1016/S2213-8587(15)00368-X
CrossRef - PubMed - Opelz G, Zeier M, Laux G, Morath C, Döhler B. No improvement of patient or graft survival in transplant recipients treated with angiotensin-converting enzyme inhibitors or angiotensin II type 1 receptor blockers: a collaborative transplant study report. J Am Soc Nephrol. 2006;17(11):3257-3262. doi:10.1681/ASN.2006050543
CrossRef - PubMed - Hiremath S, Fergusson DA, Fergusson N, Bennett A, Knoll GA. Renin-angiotensin system blockade and long-term clinical outcomes in kidney transplant recipients: a meta-analysis of randomized controlled trials. Am J Kidney Dis. 2017;69(1):78-86. doi:10.1053/j.ajkd.2016.08.018
CrossRef - PubMed - Cheungpasitporn W, Thongprayoon C, Mao MA, Kittanamongkolchai W, Sathick IJ, Erickson SB. The effect of renin-angiotensin system inhibitors on kidney allograft survival: a systematic review and meta-analysis. N Am J Med Sci. 2016;8(7):291-296. doi:10.4103/1947-2714.187141
CrossRef - PubMed - Demir ME, Özler TE, Merhametsiz Ö, et al. The results of SGLT-2 inhibitors use in kidney transplantation: 1-year experiences from two centers. Int Urol Nephrol. 2023;55(11):2989-2999. doi:10.1007/s11255-023-03645-7
CrossRef - PubMed - Angjeli A, Montada-Atin T, Nisenbaum R, et al. Single center experience with sodium-glucose co-transporter-2 inhibitors (SGLT2i) in kidney transplant recipients with diabetes. Can J Kidney Health Dis. 2024;11:1-8. doi:10.1177/20543581241293202
CrossRef - PubMed - Sánchez Fructuoso AI, Raba AB, Deras EB, et al. Sodium-glucose cotransporter-2 inhibitor therapy in kidney transplant patients with type 2 or post-transplant diabetes: an observational multicentre study. Clin Kidney J. 2023;16(6):1022-1034. doi:10.1093/ckj/sfad007
CrossRef - PubMed - Lim JH, Kwon S, Jeon Y, et al. The efficacy and safety of SGLT2 inhibitor in diabetic kidney transplant recipients. Transplantation. 2022;106(9):e404-e412. doi:10.1097/TP.0000000000004228
CrossRef - PubMed - Sheu JY, Chang LY, Chen JY, et al. The outcomes of SGLT-2 inhibitor utilization in diabetic kidney transplant recipients. Nat Commun. 2024;15(1):10043. doi:10.1038/s41467-024-54171-8
CrossRef - PubMed - Oliveras L, Montero N, Cruzado JM. Searching in the maze: sodium–glucose cotransporter-2 inhibitors in kidney transplant recipients to improve survival. Clin Kidney J. 2023;16(6):909-913. doi:10.1093/ckj/sfad045
CrossRef - PubMed - Akbari A, Fergusson D, Kokolo MB, et al. Spot urine protein measurements in kidney transplantation: a systematic review of diagnostic accuracy. Nephrol Dial Transplant. 2014;29(4):919-926. doi:10.1093/ndt/gft520
CrossRef - PubMed

Volume : 24
Issue : 8
Pages : 600 - 607
DOI : 10.6002/ect.2025.0149
From the 1Department of Internal Medicine and the 2Department of Nephrology, Ankara University Faculty of Medicine, Ankara, Türkiye
Acknowledgements: We thank Serdar Sezer for statistical support. The preliminary data of this study have been presented at “17th BANTAO congress (OP-13)” and produced from the thesis of Mihriban Güngör. The authors have not received any funding or grants in support of the presented research or for the preparation of this work and have no declarations of potential conflicts of interest.
Corresponding author: Gizem Kumru, Ankara University Faculty of Medicine, Ibni Sina Hospital, Department of Nephrology, Talatpasa Blv No:82, 06230 Altındag/Ankara, Türkiye
E-mail: gkumru@ankara.edu.tr
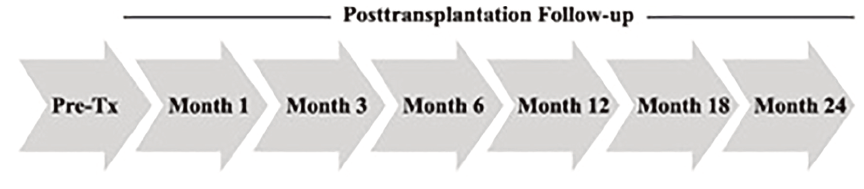
Figure 1. Timeline of Proteinuria Assessment After Kidney Transplant
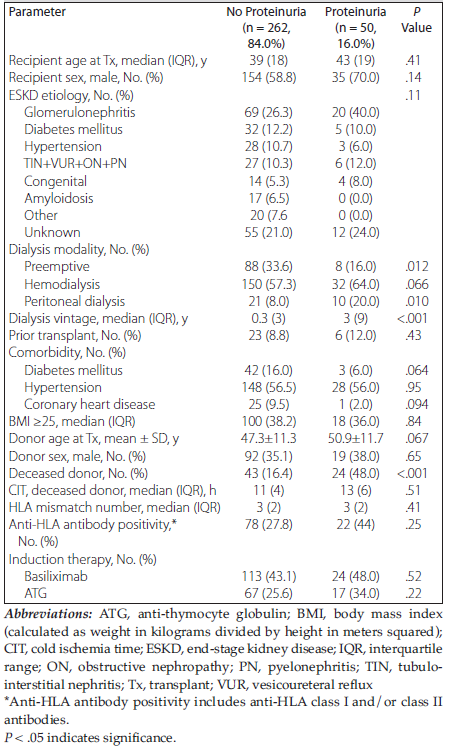
Table 1. Baseline Demographic and Clinical Data of Patients, According to Persistent Proteinuria Status (n = 312)
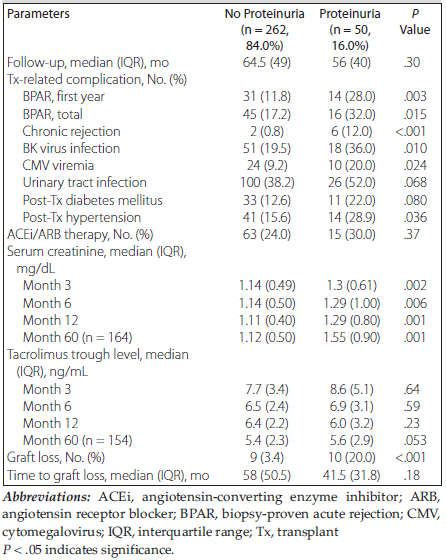
Table 2. Follow-up Data of Patients, According to Persistent Proteinuria Status (n = 312)
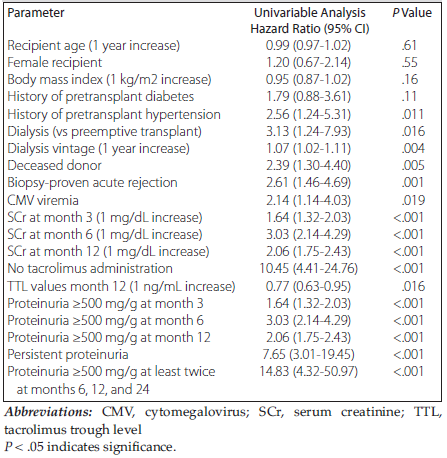
Table 3. Univariable Analysis of Factors Associated with Kidney Allograft Survival
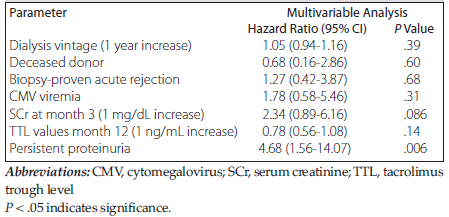
Table 4. Multivariable Analysis of Factors Associated with Kidney Allograft Survival
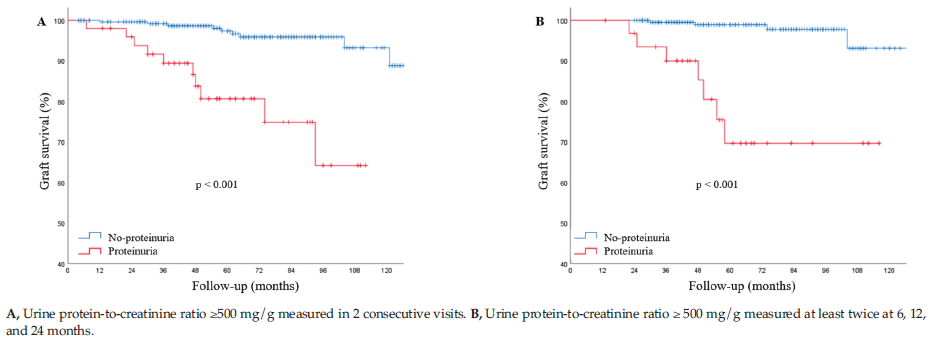
Figure 2. Kaplan-Meier plot Showing Graft Survival By Proteinuria Status
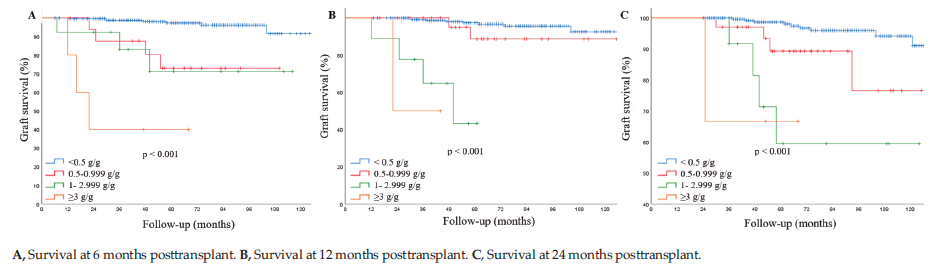
Figure 3. Kaplan-Meier Graft Survival Curves Stratified By Urine Protein-To-Creatinine Ratio Measured