Volume: 21 Issue: 5 May 2023
FULL TEXT
Objectives: Acute kidney injury after liver transplant results from several interconnected factors related to graft, recipient, intraoperative, and postoperative events. The random decision forest model enables an appreciation of each factor’s contribution, which may be helpful in setting up a preventive strategy. This study aimed to evaluate the importance of covariates at different times (pretransplant, end of surgery, postoperative day 7) with a random forest permu-tation algorithm.
Materials and Methods: We used a retrospective single-center cohort of patients, without preoperative renal failure, who underwent primary liver transplants from deceased donors (N = 1104). Significant covariates for stage 2-3 acute kidney injury were included in a random forest model, and features importance was evaluated with mean decrease accuracy and Gini index.
Results: Stage 2-3 acute kidney injury occurred in 200 patients (18.1%) and was associated with lower patient survival, even after exclusion of early graft loss. At univariate analysis, recipient factors (serum creatinine level, Model for End-Stage Liver Disease score, body weight, body mass index), graft variables (weight, macrosteatosis), intraoperative factors (number of red blood cells, duration of surgery, cold ischemia time), and postoperative event (graft dysfunction) were associated with kidney failure. The pretransplant model found that macrosteatosis and graft weight contributed to acute kidney injury. The postoperative model indicated that graft dysfunction and the number of intraoperative packed red blood cells were ranked as the 2 most essential factors in posttransplant renal failure.
Conclusions: The application of a random forest feature identified graft dysfunction, even transient and reversible, and the number of intraoperative packed red blood cells as the 2 most crucial contributors to acute kidney injury, thus indicating that prevention of graft dysfunction and bleeding are key points to limit the risk of renal failure after liver transplant.
Key words : Fatty livers, Liver transplantation, Macrosteatosis, Microsteatosis, Steatotic grafts
Introduction
In the field of liver transplantation (LT), acute kidney injury (AKI) has gained considerable interest because of its deleterious consequences on early and long-term outcomes.1-3 Post-LT AKI is a complication favored by several risk factors, often correlated.4
A better understanding of the importance of each factor according to each step of LT (preoperative, intraoperative, postoperative) would be helpful to define preventive measures and mitigate the risk of AKI. Several risk factors of AKI related to graft, recipients, and intraoperative and postoperative events, such as graft dysfunction, have been identified.5-9 These predictors have been subsequently used to build predictive algorithms or nomograms. However, most available models are often difficult to interpret or rely on linearity assumptions that cannot be verified.10-13
Random forest (RF) is a machine learning algorithm, widely used in numerous biomedical fields. One of its advantage is its ability to measure the importance of each covariate contribution, which is a helpful tool to provide hindsight about the relevancy of risk factors.14-17
Rather than building yet another model, seldom used in our routine procedures, we proposed to assess the importance of each covariate for AKI in a cohort of primary LT patients with a RF-based approach.
Materials and Methods
Study population
We considered all consecutive patients who underwent a primary LT from donation after brain death between 2006 and 2018 at the Paul Brousse Hospital, Villejuif, France. Patients with an estimated glomerular filtration rate lower than 30 mL/min (calculated according to the whole age spectrum equation)18 the day of the LT or the day before, or who required pre-LT renal replacement therapy (RRT), or who underwent combined liver-kidney transplant, or patients with fulminant hepatitis were excluded.
Recipient data were extracted from our pros-pectively maintained database, and donor infor-mation was obtained from the Cristal database, maintained by the Agence de la Biomédecine, the national organization in charge of organ allocation in France. This study was performed in accordance with French legislation and the Declaration of Helsinki.
Main definitions
We considered as clinically relevant all patients with stages 2 and 3 AKI (AKI 2-3), defined by an increase of 2-fold to 2.9-fold from baseline for stage 2 or an increase ≧3 fold from baseline or an increase in serum creatinine to ≧354 µmol/L or RRT for stage 3 (AKI 3+), according to the Kidney Disease Improving Global Outcomes guidelines, by using the sole serum creatinine level.19 The value of diuresis was not available retrospectively and was therefore not considered.
Operative technique and institutional policy with regard to steatotic graft
Surgical techniques and management after LT in our center have been described previously.20,21 A liver graft biopsy was systematically performed. A frozen section examination was done when the macroscopic aspect of the donor liver was suggestive of moderate to severe steatosis. Steatosis was assessed by expert pathologists using the preimplant biopsy or, if unavailable, liver graft reperfusion biopsy. Grafts with more than 50% macrosteatosis on frozen section biopsy were usually discarded.
Posttransplant management
The RRT after LT was indicated to treat AKI-associated complications: hyperkalemia (>6 mmol/L), hyperuricemia (>30 mmol/L), metabolic acidosis (pH <7.2), or fluid overload or anuria. Since 2012, immuno-suppression protocol consisting of basiliximab-based induction and delayed introduction of tacrolimus (days 2 and 3) was applied to patients with intraoperative risk factors of renal injury such as caval replacement or oliguria.22
Statistical analyses
The analysis was performed with R (version 3.6.1), a language and environment for statistical computing (R Foundation for Statistical Computing).
The variables with a maximum of 10% missing values were treated by a single imputation with the predictive mean matching algorithm (mice software package). Variables with more than 10% missing values were not studied.
Feature importance with random forest model
We used the RF model, known for its good predictive performance and low overfitting but also its ability to compute the importance of each variable, ie, how much each variable weighs in the decision. This latter advantage makes it easier for interpretation compared with linear models.23 Also, RF requires no assumption about the linear relationship between the covariate and the event of interest, contrary to linear models.
Feature importance has been used in several other fields.14-17 Variable importance was evaluated with the rfPermute software package according to 2 metrics: permutation importance given by the mean decrease accuracy (MDA) and mean Gini decrease. The MDA basically reflects the decrease in model accuracy when shuffling the data. The MDA positively correlates the importance of the variable. The Gini index decrease evaluates the frequency at which any new record may be misclassified at a given node in a decision tree. The number of training trees for feature importance analysis was set to 100 with 50 replications.
An approach based on RF permutations was used to estimate the significance of MDA. By permuting 50 times the response variable in the RF model (1 new RF model built at each permutation step), we could get an estimated significance of the importance metrics and obtain the P value for each variable (rfPermute software package). Although this permutational approach is computa-tionally more expensive, results are thought to be more reliable.24
Highly correlated variables were not included in the same model, because the interpretation of important features may be misleading in the case of collinearity. A preliminary evaluation of collinearity was done with the ggcorplot software package.
Overall methodology
Survival probabilities were calculated and repre-sented according to Kaplan-Meier method, and the log-rank test was used to compare survival. Identification of variables associated with AKI 2-3 was made with univariate analysis. Continuous variables were compared with the t test, and categorical variables were compared with the chi-square test or Fisher test, as appropriate.
A correlation matrix of all significant covariates was computed with the Pearson method for all pairwise observations (stats and ggcorplot software packages).
Variables with P < .05 at univariate analysis were included in the RF model. In the case of correlated variables (Pearson coefficient >0.4), the most important variable was retained, because RF permutation is very sensitive to correlated variables.
We then ran successively 3 RF models (pre-LT, end of surgery, postoperative day 7) and computed the features importance of each model. The pre-LT model included variables related to the graft or recipient at the time of LT.
Significant variables for MDA of the pre-LT model were added to the “end-surgery” model, including intraoperative variables. Significant variables with low correlation coefficients were introduced into the postoperative day 7 model, including early allograft dysfunction (EAD) defined according to Olthoff criteria.25 Since EAD included early graft loss, an event highly associated with renal failure, the postoperative day 7 model was applied to the cohort of patients alive and retransplant-free at 15 days. This selection makes it possible to better appreciate the real significance of transient and reversible graft dysfunction. Each final model included variables with a significant P value for MDA.
Results
Our cohort included 1104 patients. Of them, AKI 2-3 occurred in 200 (18.1%) patients.
Prognostic impact of stage 2-3 acute kidney injury
The AKI 2-3 was associated with lower patient survival (5-year survival rate of 70% vs 79%; P = .006). A similar finding was observed in the group of patients alive and retransplant-free at 15 day. (5-year survival rate of 73% vs 79%; P = .038), as shown in (Figure 1).
Factors associated with stage 2-3 acute kidney injury: univariate analysis
The comparisons of the data with regard to recipient and donor characteristics, intraoperative data, and outcomes according to AKI 2-3 are detailed in (Table 1). Briefly, recipients who developed AKI 2-3 had a higher Model for End-Stage Liver Disease (MELD) score and were more often in the intensive care unit at the time of LT. The AKI 2-3 was associated with higher donor body weight, larger graft, and a higher percentage of macrosteatosis but not microsteatosis. Caval replacement, length of surgery, number of packed red blood cells transfused, and cold ischemia time were also significantly associated with AKI 2-3. Recipients with AKI 2-3 experienced worse outcomes, with significantly higher rates of early graft dysfunction and 90-day mortality.
Correlations among factors associated with acute kidney injury
The correlation matrix of significant variables at univariate analysis is represented in (Figure 2). Correlated variables (Pearson coefficient >0.4) were donor body weight and graft weight and recipient body mass index and recipient body weight.
Pre-LT model: recipient-related and graft-related variables
(Figure 3A) indicates the feature importance of recipient-related and graft-related variables, ranked according to MDA. For recipient variables, the pretransplant contributors to AKI were preoperative serum creatinine level, MELD score, and body weight; for graft-related factors, the pretransplant contributors were macrosteatosis ≧30% (cutoff often used in the literature)26,27 and graft weight.
End-surgery model
The importance metrics of the end-surgery model are given in (Figure 3B). It appears that the number of packed RBCs ranked as the most critical factor at the end of transplant. Cold ischemia time exhibited a similar important MDA value compared with serum creatinine and graft weight.
Postoperative day 7 model
The feature importance of this last model is provided in (Figure 3C). An EAD appears to be the most important contributor, followed by the number of intraoperative RBC. Cold ischemia time and serum creatinine level remain significant contributors to the model.
Discussion
The negative influence of AKI on early outcomes after LT and on the long-term renal prognosis is well established28-30 and is confirmed here even in patients who survived without retransplant to the early posttransplant period. The development of AKI results from many correlated factors whom respective values weights is difficult to appreciate. To better understand the importance of each factor, we proposed a features importance analysis at different timing of LT based on RF models.
The pre-LT model indicates that most important predictors related to the recipient factor are serum creatinine level, MELD score, and body weight. These findings are not surprising, because estimated glomerular filtration used to calculate variations and define AKI depends on pretransplant serum creatinine level and body weight. The link between MELD and AKI has been already recognized in several previous studies.7,31-33 Even in our selected cohort (ie, without severe chronic renal insufficiency or acute renal failure), MELD contributed to the model, thus indicating that the severity of liver disease impairs post-LT renal function.
In the pre-LT model, the 2 most important graft-related predictors were graft weight and macros-teatosis ≧30%. Several previous studies have found a link between graft steatosis and posttransplant kidney failure. In a matched case-control study, McCormack and colleagues found 35% rate of renal failure among 20 recipients of grafts with severe steatosis versus 5% in the control group.34 In another cohort of 511 LTs, AKI occurred in 52% of cases with graft macrosteatosis >30% versus 17% in others.27
We found that the intraoperative number of packed RBCs and EAD were the most important variables in the posttransplant model of AKI 2-3. Transfusion and blood loss are common risk factors for AKI,7,32 and the number of packed RBCs can be interpreted as a reliable surrogate of surgical difficulty and hemodynamic instability. The importance of EAD was underlined previously and is biologically supported by the deleterious effects of ischemia-reperfusion injury on renal function. Previous studies showed that postreperfusion transaminase release is the strongest predictor of posttransplant renal dysfunction.32,35 Experimental data indicated that the systemic release of cytokines by Kupffer cells and attenuated induction of renal heme oxygenase 1 (an enzyme with antioxidative function) secondary to ischemia-reperfusion injury impairs creatinine clearance.36 In our work, the fact that important variables (MELD score, graft weight, steatosis, cold ischemia time)37-40 are also well-known EAD risk factors suggests that graft dysfunction, even transient and reversible, plays a central role in the alteration of posttransplant kidney function.
Reduction of the risk of EAD is critical for prevention of AKI. Therefore, strategies to alleviate ischemia-reperfusion injuries will carry protective effects on the kidney. From this perspective, end-ischemic hypothermic oxygenated perfusion of the graft, a safe and reproducible technique,41 evaluated in 3 recent randomized trials, was shown to decrease the risk of EAD42,43 and the risk of AKI.44 Reduction of cold ischemia time, with improved logistics, may also be an efficient strategy, especially in macrosteatotic grafts.38,45 Tailoring the immunosup-pressive regimen may be another way to limit early and long-term renal damage related to the transplant factors mentioned above. Several prospective studies have shown that lower exposure to tacrolimus in the early posttransplant period improves the glomerular filtration rate.46-48
Our study had several limitations. First, our study population is monocentric, and the analysis is retrospective. Measurements of urine output were not available. In addition, the management of recipients has evolved during the study period. The timing of tacrolimus introduction and the intraoperative hemodynamic management may be potential confounding factors that could not be studied here.49,50
Conclusions
Post-LT AKI 2-3 is associated with decreased survival, even among patients alive and retransplant-free 15 days after LT. The most important factors of AKI that can be potentially modulated are EAD, the number of RBCs, and cold ischemia time. Any pragmatic preventive strategy should focus on decreasing intraoperative blood loss, graft perfusion with HOPE protocol, and logistics for enabling short cold ischemia time.
References:
- Chiu PF, Lin PR, Tsai CC, Hsieh YP. The impact of acute kidney injury with or without recovery on long-term kidney outcome in patients undergoing living liver transplantation. Nephrol Dial Transplant. 2023;10.1093/ndt/gfad005. doi:10.1093/ndt/gfad005
CrossRef - PubMed - DellaVolpe J, Al-Khafaji A. Acute kidney injury before and after liver transplant. J Intensive Care Med. 2019;34(9):687-695. doi:10.1177/0885066618790558
CrossRef - PubMed - Kundakci A, Pirat A, Komurcu O, et al. Rifle criteria for acute kidney dysfunction following liver transplantation: incidence and risk factors. Transplant Proc. 2010;42(10):4171-4174. doi:10.1016/j.transproceed.2010.09.137
CrossRef - PubMed - Durand F, Francoz C, Asrani SK, et al. Acute kidney injury after liver transplantation. Transplantation. 2018;102(10):1636-1649. doi:10.1097/TP.0000000000002305
CrossRef - PubMed - Wadei HM, Lee DD, Croome KP, et al. Early allograft dysfunction after liver transplantation is associated with short- and long-term kidney function impairment. Am J Transplant. 2016;16(3):850-859. doi:10.1111/ajt.13527
CrossRef - PubMed - Sharma P, Welch K, Eikstadt R, Marrero JA, Fontana RJ, Lok AS. Renal outcomes after liver transplantation in the model for end-stage liver disease era. Liver Transpl. 2009;15(9):1142-1148. doi:10.1002/lt.21821
CrossRef - PubMed - Utsumi M, Umeda Y, Sadamori H, et al. Risk factors for acute renal injury in living donor liver transplantation: evaluation of the RIFLE criteria. Transpl Int. 2013;26(8):842-852. doi:10.1111/tri.12138
CrossRef - PubMed - Kalisvaart M, de Haan JE, Hesselink DA, et al. The postreperfusion syndrome is associated with acute kidney injury following donation after brain death liver transplantation. Transpl Int. 2017;30(7):660-669. doi:10.1111/tri.12891
CrossRef - PubMed - Leithead JA, Ferguson JW. Chronic kidney disease after liver transplantation. J Hepatol. 2015;62(1):243-244. doi:10.1016/j.jhep.2014.08.054
CrossRef - PubMed - Kalisvaart M, Schlegel A, Umbro I, et al. The AKI prediction score: a new prediction model for acute kidney injury after liver transplantation. HPB (Oxford). 2019;21(12):1707-1717. doi:10.1016/j.hpb.2019.04.008
CrossRef - PubMed - Lee HC, Yoon SB, Yang SM, et al. Prediction of acute kidney injury after liver transplantation: machine learning approaches vs. logistic regression model. J Clin Med. 2018;7(11). doi:10.3390/jcm7110428
CrossRef - PubMed - Bao B, Wang W, Wang Y, Chen Q. A prediction score model and survival analysis of acute kidney injury following orthotopic liver transplantation in adults. Ann Palliat Med. 2021;10(6):6168-6179. doi:10.21037/apm-21-842
CrossRef - PubMed - Xu X, Ling Q, Wei Q, et al. An effective model for predicting acute kidney injury after liver transplantation. Hepatobiliary Pancreat Dis Int. 2010;9(3):259-263.
CrossRef - PubMed - Hanson HA, Martin C, O’Neil B, et al. The relative importance of race compared to health care and social factors in predicting prostate cancer mortality: a random forest approach. J Urol. 2019;202(6):1209-1216. doi:10.1097/JU.0000000000000416
CrossRef - PubMed - Basnet TB, G CS, Basnet R, Neupane B. Dietary nutrients of relative importance associated with coronary artery disease: public health implication from random forest analysis. PLoS One. 2020;15(12):e0243063. doi:10.1371/journal.pone.0243063
CrossRef - PubMed - Thongprayoon C, Jadlowiec CC, Leeaphorn N, et al. Feature importance of acute rejection among black kidney transplant recipients by utilizing random forest analysis: an analysis of the UNOS database. Medicines (Basel). 2021;8(11). doi:10.3390/medicines8110066
CrossRef - PubMed - Phung VLH, Oka K, Hijioka Y, Ueda K, Sahani M, Wan Mahiyuddin WR. Environmental variable importance for under-five mortality in Malaysia: a random forest approach. Sci Total Environ. 2022;845:157312. doi:10.1016/j.scitotenv.2022.157312
CrossRef - PubMed - Pottel H, Hoste L, Dubourg L, et al. An estimated glomerular filtration rate equation for the full age spectrum. Nephrol Dial Transplant. 2016;31(5):798-806. doi:10.1093/ndt/gfv454
CrossRef - PubMed - Khwaja A. KDIGO clinical practice guidelines for acute kidney injury. Nephron Clin Pract. 2012;120(4):c179-c184. doi:10.1159/000339789
CrossRef - PubMed - Rajakannu M, Awad S, Ciacio O, et al. Intention-to-treat analysis of percutaneous endovascular treatment of hepatic artery stenosis after orthotopic liver transplantation. Liver Transpl. 2016;22(7):923-933. doi:10.1002/lt.24468
CrossRef - PubMed - Allard MA, Lopes F, Frosio F, et al. Extreme large-for-size syndrome after adult liver transplantation: a model for predicting a potentially lethal complication. Liver Transpl. 2017;23(10):1294-1304. doi:10.1002/lt.24835
CrossRef - PubMed - Saliba F, Duvoux C, Gugenheim J, et al. Efficacy and safety of everolimus and mycophenolic acid with early tacrolimus withdrawal after liver transplantation: a multicenter randomized trial. Am J Transplant. 2017;17(7):1843-1852. doi:10.1111/ajt.14212
CrossRef - PubMed - Breiman L. Random forests. Machine Learning. 2001;45:5-32. doi:10.1023/A:1010933404324
CrossRef - PubMed - Strobl C, Boulesteix AL, Zeileis A, Hothorn T. Bias in random forest variable importance measures: illustrations, sources and a solution. BMC Bioinformatics. 2007;8:25. doi:10.1186/1471-2105-8-25
CrossRef - PubMed - Olthoff KM, Kulik L, Samstein B, et al. Validation of a current definition of early allograft dysfunction in liver transplant recipients and analysis of risk factors. Liver Transpl. 2010;16(8):943-949. doi:10.1002/lt.22091
CrossRef - PubMed - Dutkowski P, Schlegel A, Slankamenac K, et al. The use of fatty liver grafts in modern allocation systems: risk assessment by the balance of risk (BAR) score. Ann Surg. 2012;256(5):861-868; discussion 868-869. doi:10.1097/SLA.0b013e318272dea2
CrossRef - PubMed - Jadlowiec C, Smith M, Neville M, et al. Acute kidney injury patterns following transplantation of steatotic liver allografts. J Clin Med. 2020;9(4). doi:10.3390/jcm9040954
CrossRef - PubMed - Barri YM, Sanchez EQ, Jennings LW, et al. Acute kidney injury following liver transplantation: definition and outcome. Liver Transpl. 2009;15(5):475-483. doi:10.1002/lt.21682
CrossRef - PubMed - Watt KD, Pedersen RA, Kremers WK, Heimbach JK, Charlton MR. Evolution of causes and risk factors for mortality post-liver transplant: results of the NIDDK long-term follow-up study. Am J Transplant. 2010;10(6):1420-1427. doi:10.1111/j.1600-6143.2010.03126.x
CrossRef - PubMed - Ayhan A, Ersoy Z, Ulas A, Zeyneloglu P, Pirat A, Haberal M. Incidence and patient outcomes in renal replacement therapy after orthotopic liver transplant. Exp Clin Transplant. 2017;15(Suppl 1):258-260. doi:10.6002/ect.mesot2016.P126
CrossRef - PubMed - Leithead JA, Rajoriya N, Gunson BK, Muiesan P, Ferguson JW. The evolving use of higher risk grafts is associated with an increased incidence of acute kidney injury after liver transplantation. J Hepatol. 2014;60(6):1180-1186. doi:10.1016/j.jhep.2014.02.019
CrossRef - PubMed - Park MH, Shim HS, Kim WH, et al. Clinical risk scoring models for prediction of acute kidney injury after living donor liver transplantation: a retrospective observational study. PLoS One. 2015;10(8):e0136230. doi:10.1371/journal.pone.0136230
CrossRef - PubMed - Romano TG, Schmidtbauer I, Silva FM, Pompilio CE, D’Albuquerque LA, Macedo E. Role of MELD score and serum creatinine as prognostic tools for the development of acute kidney injury after liver transplantation. PLoS One. 2013;8(5):e64089. doi:10.1371/journal.pone.0064089
CrossRef - PubMed - McCormack L, Petrowsky H, Jochum W, Mullhaupt B, Weber M, Clavien PA. Use of severely steatotic grafts in liver transplantation: a matched case-control study. Ann Surg. 2007;246(6):940-946; discussion 946-948. doi:10.1097/SLA.0b013e31815c2a3f
CrossRef - PubMed - Leithead JA, Tariciotti L, Gunson B, et al. Donation after cardiac death liver transplant recipients have an increased frequency of acute kidney injury. Am J Transplant. 2012;12(4):965-975. doi:10.1111/j.1600-6143.2011.03894.x
CrossRef - PubMed - Tanaka Y, Maher JM, Chen C, Klaassen CD. Hepatic ischemia-reperfusion induces renal heme oxygenase-1 via NF-E2-related factor 2 in rats and mice. Mol Pharmacol. 2007;71(3):817-825. doi:10.1124/mol.106.029033
CrossRef - PubMed - Levesque E, Duclos J, Ciacio O, Adam R, Castaing D, Vibert E. Influence of larger graft weight to recipient weight on the post-liver transplantation course. Clin Transplant. 2013;27(2):239-247. doi:10.1111/ctr.12059
CrossRef - PubMed - Stahl JE, Kreke JE, Malek FA, Schaefer AJ, Vacanti J. Consequences of cold-ischemia time on primary nonfunction and patient and graft survival in liver transplantation: a meta-analysis. PLoS One. 2008;3(6):e2468. doi:10.1371/journal.pone.0002468
CrossRef - PubMed - Addeo P, Noblet V, Naegel B, Bachellier P. Large-for-size orthotopic liver transplantation: a systematic review of definitions, outcomes, and solutions. J Gastrointest Surg. 2020;24(5):1192-1200. doi:10.1007/s11605-019-04505-5
CrossRef - PubMed - Manzia TM, Lai Q, Hartog H, et al. Graft weight integration in the early allograft dysfunction formula improves the prediction of early graft loss after liver transplantation. Updates Surg. 2022;74(4):1307-1316. doi:10.1007/s13304-022-01270-0
CrossRef - PubMed - Patrono D, Lavezzo B, Molinaro L, et al. Hypothermic oxygenated machine perfusion for liver transplantation: an initial experience. Exp Clin Transplant. 2018;16(2):172-176. doi:10.6002/ect.2016.0347
CrossRef - PubMed - Ravaioli M, Germinario G, Dajti G, et al. Hypothermic oxygenated perfusion in extended criteria donor liver transplantation: a randomized clinical trial. Am J Transplant. 2022;22(10):2401-2408. doi:10.1111/ajt.17115
CrossRef - PubMed - Czigany Z, Pratschke J, Fronek J, et al. Hypothermic oxygenated machine perfusion reduces early allograft injury and improves post-transplant outcomes in extended criteria donation liver transplantation from donation after brain death: results from a multicenter randomized controlled trial (HOPE ECD-DBD). Ann Surg. 2021;274(5):705-712. doi:10.1097/SLA.0000000000005110
CrossRef - PubMed - Schlegel A, Mueller M, Muller X, et al. A multicenter randomized-controlled trial of hypothermic oxygenated perfusion (HOPE) for human liver grafts before transplantation. J Hepatol. 2023;78(4):783-793. doi:10.1016/j.jhep.2022.12.030
CrossRef - PubMed - Westerkamp AC, de Boer MT, van den Berg AP, Gouw AS, Porte RJ. Similar outcome after transplantation of moderate macrovesicular steatotic and nonsteatotic livers when the cold ischemia time is kept very short. Transpl Int. 2015;28(3):319-329. doi:10.1111/tri.12504
CrossRef - PubMed - Saliba F, Duvoux C, Dharancy S, et al. Early switch from tacrolimus to everolimus after liver transplantation: outcomes at 2 years. Liver Transpl. 2019;25(12):1822-1832. doi:10.1002/lt.25664
CrossRef - PubMed - Lin M, Mittal S, Sahebjam F, Rana A, Sood GK. Everolimus with early withdrawal or reduced-dose calcineurin inhibitors improves renal function in liver transplant recipients: A systematic review and meta-analysis. Clin Transplant. 2017;31(2). doi:10.1111/ctr.12872
CrossRef - PubMed - Kadry Z, Stine JG, Dohi T, et al. Renal protective effect of everolimus in liver transplantation: a prospective randomized open-label trial. Transplant Direct. 2021;7(7):e709. doi:10.1097/TXD.0000000000001159
CrossRef - PubMed - Saez de la Fuente I, Saez de la Fuente J, Martin Badia I, et al. Postoperative blood pressure deficit and acute kidney injury after liver transplant. Exp Clin Transplant. 2022;20(11):992-999. doi:10.6002/ect.2022.0272
CrossRef - PubMed - Bhatia R, Fabes J, Krzanicki D, Rahman S, Spiro M. Association between fast-track extubation after orthotopic liver transplant, postoperative vasopressor requirement, and acute kidney injury. Exp Clin Transplant. 2021;19(4):339-344. doi:10.6002/ect.2020.0422
CrossRef - PubMed

Volume : 21
Issue : 5
Pages : 408 - 414
DOI : 10.6002/ect.2023.0049
From the 1AP-HP Hôpital Paul Brousse, Centre Hépato-Biliaire, Université Paris Saclay, Villejuif, France; the 2Équipe Chronothérapie, Cancers et Transplantation, Université Paris Saclay, France; the 3Department of Gastroenterological Surgery, Graduate School of Medical Sciences, Kumamoto University, Kumamoto, Japan; and the 4Unité Institut National de la Santé et de la Recherche Médicale 1193, Villejuif, France
Acknowledgements: The authors have not received any funding or grants in support of the presented research or for the preparation of this work and have no declarations of potential conflicts of interest.
Corresponding author: Marc Antoine Allard, Centre Hépatobiliaire, Hôpital Paul Brousse, 14 av Paul Vaillant Couturier, 94800 Villejuif, France
Phone: +33 1 45 59 64 36
E-mail: marcantoine.allard@aphp.fr
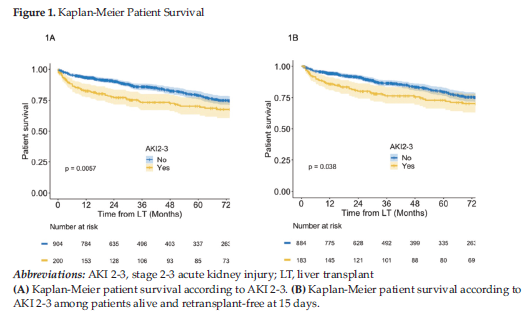
Figure 1.Kaplan-Meier Patient Survival
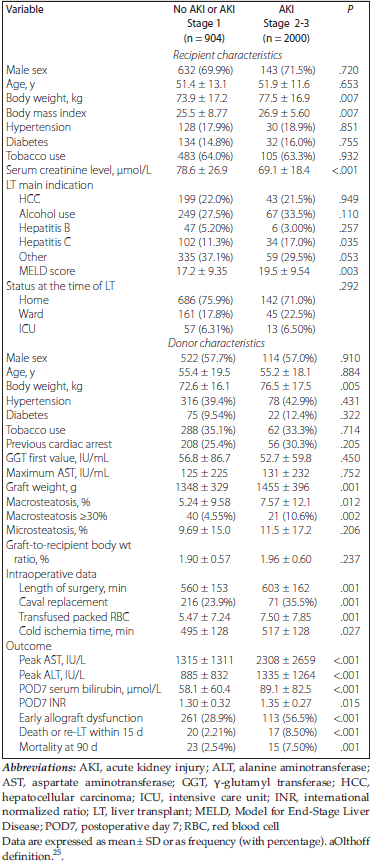
Table 1.Univariate Analysis for AKI 2-3
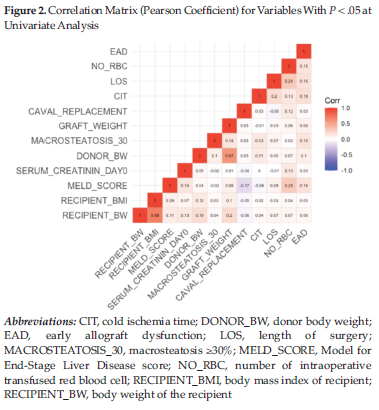
Figure 2.Correlation Matrix (Pearson Coefficient) for Variables With P < at Univariate Analysis
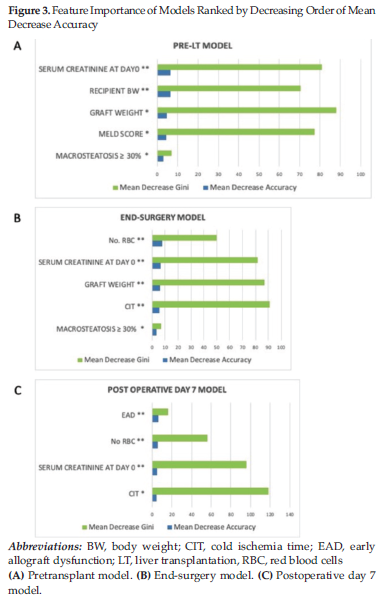
Figure 3.Feature Importance of Models Ranked by Decreasing Order of Mean Decrease Accuracy