Volume: 18 Issue: 6 November 2020
FULL TEXT
Geotrichum capitatum is a rare fungal pathogen that has infrequently affected immunocompromised patients with onco-hematologic diseases. Geotrichum capitatum invasive infection has been associated with poor prognosis, with a mortality rate ranging from 50% to 90%. Here, we report the first case of Geotrichum capitatum invasive fungal infection in a liver transplant recipient from an unrelated deceased donor, who was effectively treated with amphotericin B and voriconazole. We also reviewed the available literature in the field.
Key words : Blastoschizomyces capitatus, Invasive fungal infection, Magnusiomyces capitatus, Saprochaete capitate, Solid-organ transplantation
Introduction
Invasive fungal infections (IFI) are a common cause of severe morbidity and even mortality in immunocompromised patients.1 In the setting of liver transplant, IFIs usually occur in the perioperative phase. The most frequent IFIs are Candida albicans, Cryptococcus neoformans, and Aspergillus fumigatus.2 Geotrichum capitatum, which is also known as Blastoschizomyces capitatus (belonging to a class of saccharomycetes), has become an emerging cause of IFIs among onco-hematologic patients with severe neutropenia.3 This infection often occurs as a bloodstream infection with occasional secondary localizations, mainly in skin or lungs. Despite appropriate antifungal therapy, the mortality rate for patients with G. capitatum infection exceeds 50%.4
Here, we report the first case of G. capitatum-related invasive fungal infection in a liver transplant recipient. We also reviewed the available literature in this field.
Case Report
A 52-year-old white man with hepatitis B-delta-related cirrhosis was admitted in July 2017 to our unit for hepatic encephalopathy and hydrothorax. At admission, the patient showed Child-Pugh and Model for End-Stage Liver disease scores of 10 and 22, respectively. During hospitalization, he developed hepatorenal syndrome, which required intensive care unit (ICU) admission. The patient underwent long-term empirical antibiotic therapy for sepsis of unknown origin (meropenem 1 g at 3 times per day and vancomycin 500 mg at 4 times per day). At 2 weeks after admission, the patient underwent liver transplant. He received a full graft from an unrelated deceased female donor (cause of death was cerebral hemorrhage) in accordance with the Italian allocation system. The patient’s early post-transplant course was complicated by pneumothorax and abdominal reintervention due to biliary leak. The immunosuppressive regimen was started with steroids and basiliximab and maintained with steroids and tacrolimus.
During the early post-transplant period, the patient received prophylactic therapy with ceftazidime, tigecycline, and anidulafungin. On day 7 post-transplant, bronchoalveolar lavage and blood samples, from the central venous catheter, were obtained. Samples were inoculated on blood agar BD, chocolate agar BD, and Sabouraud agar BD solid media and incubated for 24 hours at 37°C in anaerobiosis (VITEK MS MALDI-TOF, bioMérieux, Marcy-l'Étoile, France). Laboratory results revealed G. capitatum invasive infection.
After ruling out endophthalmitis and endocarditis, the patient started a treatment with liposomal amphotericin B at 5 mg/kg/day, adding within 5 days voriconazole (at 6 mg/kg twice daily as a loading dose and then at 4 mg/kg twice daily, adjusting the dose according to serum trough levels). Dual antifungal therapy was effective, with the patient showing clinical improvement and negative results in both blood cultures and bronchoalveolar lavage. However, he developed a further episode of Enterococcus faecium-related sepsis and subsequently died from multiorgan failure.
Discussion
Geotrichum capitatum-related IFIs have rarely been reported to date.5 Neutropenia, previous or ongoing chemotherapy, and prolonged use of broad-spectrum antibiotics represent the most common risk factors in immunocompromised patients (Table 1). Conversely, both prolonged ICU stay and previous surgery are commonly described conditions among immunocompetent patients (Table 2).6,7
To date, no specific treatment algorithm for G. capitatum-related IFIs has been established. Although the first introduced treatment was liposomal amphotericin B, recently published data have reported that voriconazole,5 posaconazole,8,9 and isavuconazole10 monotherapy seemed to be equally effective.
Despite adequate antifungal treatment, outcomes of G. capitatum IFIs are generally poor. The mortality rate, ranging from 48% to 69%, reflects not only the suboptimal response to antifungal therapy but also the patient’s underlying comorbidities (Tables 1 and 2).
Invasive fungal infections can be a severe cause of morbidity and mortality in the early phase after solid-organ transplant. Due to significant changes in epidemiology, with increasing prevalence of non-albicans Candida strains, prophylactic strategies have been recently modified.2,11 Since our patient displayed several risk factors for post-transplant IFI (including ICU admission before liver transplant, preoperative Candida colonization, acute renal failure with need for renal replacement therapy, reintervention, long-term broad-spectrum antibiotic use, pleural drainage, and mechanical ventilation),4,12-14 he received prophylaxis with anidulafungin.11 Unfortunately, this treatment was not effective. In fact, G. capitatum is considered intrinsically resistant to echinocandins, and these agents have been shown to be the cause of several episodes of breakthrough infections among neutropenic patients receiving echinocandins.15
Regarding antifungal therapy, our case confirmed the effectiveness of the combination of amphotericin B and voriconazole. However, we were not able to provide significant data about dosage due to the patient’s impaired renal function and potential drug-drug interactions.
Conclusions
Here, we report the first case of a G. capitatum IFI early after liver transplant, which was not effectively prevented by echinocandin prophylaxis but effectively treated with combined amphotericin B and azole therapy. Despite prophylaxis, high-risk liver transplant recipients should be actively screened for IFI development, and they should receive early tailored therapy to avoid graft dysfunction and multiorgan involvement.
References:
- Sganga G. Fungal infections in immunocompromised patients. Mycoses. 2011;54 Suppl 4:1-3.
CrossRef - PubMed - Hogen R, Dhanireddy KK. Invasive fungal infections following liver transplantation. Curr Opin Organ Transplant. 2017;22(4):356-363.
CrossRef - PubMed - Pfaller MA, Diekema DJ. Rare and emerging opportunistic fungal pathogens: concern for resistance beyond Candida albicans and Aspergillus fumigatus. J Clin Microbiol. 2004;42(10):4419-4431.
CrossRef - PubMed - Rolston K. Overview of systemic fungal infections. Oncology (Williston Park). 2001;15(11 Suppl 9):11-14.
CrossRef - PubMed - Saghrouni F, Abdeljelil JB, Youssef YB, et al. Geotrichum capitatum septicemia in patients with acute myeloid leukemia. Report of three cases. Med Mycol Case Rep. 2012;1(1):88-90.
CrossRef - PubMed - Farina C, Vailati F, Manisco A, Goglio A. Fungaemia survey: a 10-year experience in Bergamo, Italy. Mycoses. 1999;42(9-10):543-548.
CrossRef - PubMed - Martino P, Venditti M, Micozzi A, et al. Blastoschizomyces capitatus: an emerging cause of invasive fungal disease in leukemia patients. Rev Infect Dis. 1990;12(4):570-582.
CrossRef - PubMed - Brunetti G, Visconti V, Ghezzi MC, Mantovani S, Ferretti G, Raponi G. Management and treatment of Magnusiomyces capitatus (Geotrichum capitatum) pleural infection in a non-neutropenic patient with posaconazole. A new therapeutic opportunity? New Microbiol. 2016;39(4):307-309.
CrossRef - PubMed - Pemmaraju N, Shetty AV, Prieto VG, Jain N, Kontoyiannis DP, Borthakur G. Disseminated Saprochaete capitata (formerly known as Geotrichum capitatum and Blastoschizomyces capitatus) in a patient with acute myeloid leukemia. Eur J Haematol. 2014;93(6):543-544.
CrossRef - PubMed - Esposto MC, Prigitano A, Lo Cascio G, et al. Yeast-like filamentous fungi: Molecular identification and in vitro susceptibility study. Med Mycol. 2019;57(7):909-913.
CrossRef - PubMed - Giannella M, Husain S, Saliba F, Viale P. Use of echinocandin prophylaxis in solid organ transplantation. J Antimicrob Chemother. 2018;73(suppl_1):i51-i59.
CrossRef - PubMed - De Pascale G, Tumbarello M. Fungal infections in the ICU: advances in treatment and diagnosis. Curr Opin Crit Care. 2015;21(5):421-429.
CrossRef - PubMed - Arendrup MC, Boekhout T, Akova M, Meis JF, Cornely OA, Lortholary O, European Society of Clinical M, Infectious Diseases Fungal Infection Study G, European Confederation of Medical M. ESCMID and ECMM joint clinical guidelines for the diagnosis and management of rare invasive yeast infections. Clin Microbiol Infect. 2014;20 Suppl 3:76-98.
CrossRef - PubMed - Martino R, Salavert M, Parody R, et al. Blastoschizomyces capitatus infection in patients with leukemia: report of 26 cases. Clin Infect Dis. 2004;38(3):335-341.
CrossRef - PubMed - Oya S, Muta T. Breakthrough infection of Geotrichum capitatum during empirical caspofungin therapy after umbilical cord blood transplantation. Int J Hematol. 2018;108(5):558-563.
CrossRef - PubMed - Amft N, Miadonna A, Viviani MA, Tedeschi A. Disseminated Geotrichum capitatum infection with predominant liver involvement in a patient with non Hodgkin's lymphoma. Haematologica. 1996;81(4):352-355.
CrossRef - PubMed - Christakis G, Perlorentzou S, Aslanidou M, Megalakaki A, Velegraki A. Fatal Blastoschizomyces capitatus sepsis in a neutropenic patient with acute myeloid leukemia: first documented case from Greece. Mycoses. 2005;48(3):216-220.
CrossRef - PubMed - Etienne A, Datry A, Gaspar N, et al. Successful treatment of disseminated Geotrichum capitatum infection with a combination of caspofungin and voriconazole in an immunocompromised patient. Mycoses. 2008;51(3):270-272.
CrossRef - PubMed - Bonini A, Capatti C, Parmeggiani M, et al. Galactomannan detection in Geotrichum capitatum invasive infections: report of 2 new cases and review of diagnostic options. Diagn Microbiol Infect Dis. 2008;62(4):450-452.
CrossRef - PubMed - Ikuta K, Torimoto Y, Yamamoto M, et al. Successful treatment of systemic Geotrichum capitatum infection by liposomal amphotericin-B, itraconazole, and voriconazole in a Japanese man. Intern Med. 2010;49(22):2499-2503.
CrossRef - PubMed - Gao GX, Tang HL, Zhang X, Xin XL, Feng J, Chen XQ. Invasive fungal infection caused by geotrichum capitatum in patients with acute lymphoblastic leukemia: a case study and literature review. Int J Clin Exp Med. 2015;8(8):14228-14235.
CrossRef - PubMed - Trabelsi H, Néji S, Gargouri L, et al. Geotrichum capitatum septicemia: case report and review of the literature. Mycopathologia. 2015;179(5-6):465-469.
CrossRef - PubMed - Miglietta F, Vella A, Faneschi ML, et al. Geotrichum capitatum septicaemia in a haematological patient after acute myeloid leukaemia relapse: identification using MALDI-TOF mass spectrometry and review of the literature. Infez Med. 2015;23(2):161-167.
CrossRef - PubMed - Janilionis R, Lukoševičiūtė L, Beiša V, et al. Successful management of gastropulmonary fistula due to invasive fungal infection after chemotherapy and autologous stem cell transplantation: a case report. Acta Med Litu. 2016;23(3):169-174.
CrossRef - PubMed - Tanuskova D, Horakova J, Svec P, et al. First case of invasive Magnusiomyces capitatus infection in Slovakia. Med Mycol Case Rep. 2017;16:12-15.
CrossRef - PubMed - Wills TS, Degryse A, Lavina J, Sinnott JT. Blastoschizomyces capitatus pneumonia in an immunocompetent male. South Med J. 2004;97(7):702-704.
CrossRef - PubMed - Pesut D, Adzic T, Tosic T, et al. Bilateral pulmonary shadows and incapsulated mediastinal effusion in a patient with respiratory blastoschizomycosis. Pneumologia. 2008;57(2):88, 90-91.
CrossRef - PubMed - Sreeja S, Banashankari GS, Bhavana MV, Devi DR. Blastoschizomyces capitatus pneumonia: a rare case. Indian J Pathol Microbiol. 2011;54(4):846-847.
CrossRef - PubMed - Radic M, Goic Barisic I, Kuscevic D, Novak A, Tonkic M, Rubic Z. Geotrichum capitatum respiratory tract infection in a patient with polytrauma. Infez Med. 2015;23(3):270-274.
CrossRef - PubMed - Chauhan S, Tiwari S, Singh P, Goyal R. Pulmonary Infection by Blastoschizomyces capitatus in An old Tuberculosis Patient. J Clin Diagn Res. 2015;9(9):DD01-DD02.
CrossRef - PubMed - Subramanya Supram H, Gokhale S, Chakrabarti A, Rudramurthy SM, Gupta S, Honnavar P. Emergence of Magnusiomyces capitatus infections in Western Nepal. Med Mycol. 2016;54(2):103-110.
CrossRef - PubMed - Cavanna C, Lallitto F, Mangione F, Tamarozzi F, Marone P, Ceriana P. Fungemia due to Saprochaete capitata in a non-neutropenic patient hospitalized in an intensive care unit after cardiac surgery. J Mycol Med. 2017;27(2):281-284.
CrossRef - PubMed - D'Assumpcao C, Lee B et Heidari A. A Case of Magnusiomyces capitatus Peritonitis Without Underlying Malignancies. J Investig Med High Impact Case Rep. 2018;6:2324709618795268.
CrossRef - PubMed - Tanabe MB, Patel SA. Blastoschizomyces capitatus pulmonary infections in immunocompetent patients: case report, case series and literature review. Epidemiol Infect. 2018;146(1):58-64.
CrossRef - PubMed

Volume : 18
Issue : 6
Pages : 737 - 740
DOI : 10.6002/ect.2019.0170
From the 1Multivisceral Transplant Unit, Department of Surgery, Oncology and
Gastroenterology, the 2Department of Infectious Disease, Department of Molecular
Medicine, the 3Intensive Care Unit, Department of Medicine; the 4Microbiology
and Virology Unit, Department of Molecular Medicine, and the 5Hepatobiliary
Surgery and Liver Transplantation, Department of Surgery, Oncology and
Gastroenterology, Padua University, Padua, Italy
Acknowledgements: The authors have no sources of funding for this study and have
no conflicts of interest to declare.
*Chiara Becchetti and Alberto Ferrarese contributed equally to this work.
Corresponding author: Patrizia Burra, Multivisceral Transplant Unit, Dept.
Surgery, Oncology and Gastroenterology, Padua University Hospital, via
Giustiniani 2, 35128, Padua, Italy
E-mail: burra@unipd.it
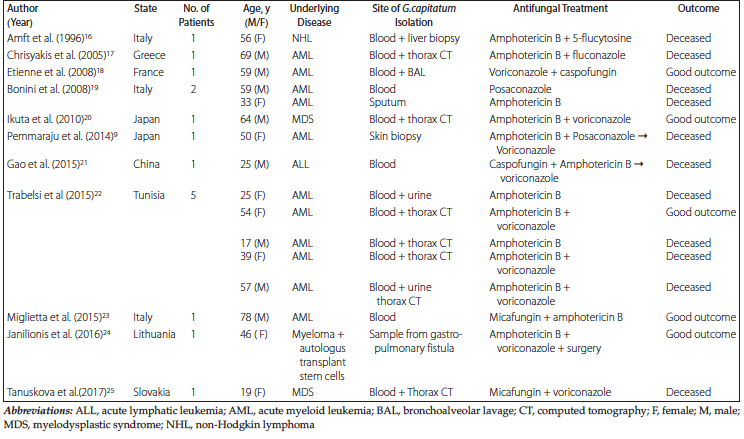
Table 1. Case Reports of Geotrichum capitatum Infections in Immunocompromised Patients (Neutropenic or With Hematologic Malignancies)
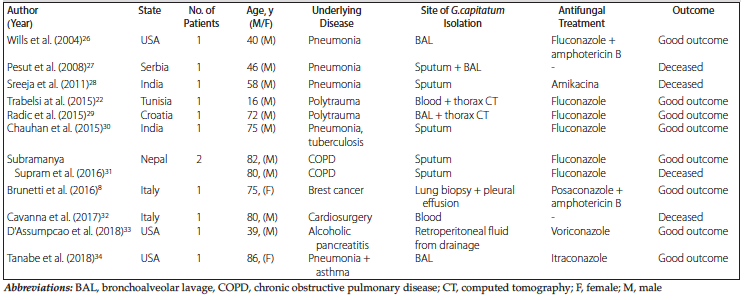
Table 2. Case Reports of Geotrichum capitatum Infections in Immunocompetent Patients