Volume: 15 Issue: 2 April 2017
FULL TEXT
Objectives: Urinary calculi rarely occur in renal transplant. However, because of peculiarities shown with renal allografts, a prudent approach is necessary to prevent further complications or even graft failure. There are no well-established guidelines for urolithiasis in renal grafts regarding adequate therapy selection. In the present article, different therapeutic interventions are discussed, including in 1 case a pyelovesicostomy as an uncommon intervention.
Materials and Methods: We retrospectively reviewed data of 1115 patients who underwent renal transplant between January 2002 and December 2014 for urolithiasis in different databases.
Results: Eight patients in our study group formed urinary calculi after renal transplant. Only 5 patients were included, with incidence rate of 0.45%, since 3 patients received transplants elsewhere. Time between transplant and diagnosis ranged from 2 to 98 months. Extracorporeal shock wave lithotripsy (50%) was the most common intervention, followed by ureterorenoscopy (29%) and percutaneous nephrolithotomy (16%). One patient required 20 interventions due to recurrent urinary stones, necessitating an alternative procedure. In this case, a pyelovesicostomy was performed (an uncommon and previously not performed procedure for urolithiasis after renal graft). All patients were stone free at last follow-up.
Conclusions: In contrast to other studies, renal stones from donors were not observed. Treatment took into account stone size, number, and localization, similar to the approach in the general population. However, alternative procedures, especially pyelovesicostomy, could be considered in patients with recurrent urolithiasis and who require multiple interventions.
Key words : Complications, Kidney transplantation, Urolithiasis
Introduction
Urologic complications after renal transplant necessitate an attentive approach because of the multiple factors contributing to high morbidity and even mortality. One possible but rare complication in the transplanted kidney is the occurrence of stones. In the literature, the incidence rate varies from 0.2% to 2.1%.1-9 With improvements in both graft and patient survival and the not negligible increase in the acceptance of marginal organs, clinicians will steadily be faced with more long-term complications, including urolithiasis, in renal grafts.10,11 There are 2 possible ways for urinary stones to evolve in an allograft. Either the calculi are present in the donor (these stones are detected perioperatively or they are considered to be, if detected later, new formations).1,2 In general, there are more de novo formations than stones from donors.1
Patients who develop stones in an allograft kidney usually do not present with typical symptoms of urolithiasis on grounds of the kidney’s denervation, which contributes to a delayed diagnosis.1,2,12 Nonetheless, to prevent further complications like sepsis, graft rejection, or significant graft impairment, early diagnosis and treatment are necessary. After diagnosis, treatment of calculi in the allograft kidney is challenging because of multiple factors. On the one hand, the kidney’s heterotopic position in the iliac fossa requires an altered interventional procedure, which clinicians are often not accustomed to. On the other hand, considering the weakened immune system and the impaired wound healing, clinicians justifiably fear peri-interventional complications in the patient’s solely functioning kidney.2,12,13
Therapeutic interventions for urolithiasis implemented in the renal graft include extracorporeal shock wave lithotripsy (ESWL), percutaneous nephrolithotomy (PNL), ureterorenoscopy, and open surgery. In some cases, conservative procedures are used.1,2 In addition to these procedures, as shown here in 1 patient with secondary oxalosis and recurrence of urinary stones, a pyelovesicostomy was implemented, an uncommon and not yet discussed therapeutic intervention for patients with urolithiasis in the renal graft.
State-of-the-art technology has enabled the detection of even small caliculi. This could lead to the acceptance of donors having urinary stones. Kidneys with stones can be managed before, during, or after transplant.14 To date, most publications are either case reports or have presented just 1 therapy option; therefore, there is a lack of international, well-established guidelines for urolithiasis in the renal graft. Treatment options for donors are not different from those for patients presenting with urinary stones in their native kidney. Here, our aim was to discuss different therapy options for urolithiasis in the renal graft, with consideration of alternative therapeutic interventions, based on data from the Urology Department at the Charité University Hospital in Campus Mitte.
Materials and Methods
This study followed the Statute of the Charité-University Hospital Berlin ensuring Good Scientific Practice of June 2012 (version May 2014).
Data from kidney recipients with urinary stones after kidney transplant were retrospectively collected and reviewed from 2 different databases at the Department of Urology in Campus Mitte.
Patient data were recorded with regard to privacy protection and anonymization. One database contained all medical records archived during the past decade at the Charité University Hospital, whereas the other database was specifically created to collect and follow patients with renal allografts.
We collected the following information: age and sex, data on transplant techniques, diagnostic imaging results at time of diagnosis and before and after transplant, and patient symptoms contributing to diagnosis. Interventional procedures after diagnosis, stone localization, stone composition and size, outcome, and current transplant function were also collected.
Databases were searched for patients with urinary stones. Patients not transplanted but diagnosed with urolithiasis at the Urology Department Campus Mitte were also included. For transplant, the renal artery and vein were anastomosed end-to-side with the iliac vessels, placing the allograft either in the right or in the left iliac fossa. In addition, ureterocystoneostomy involved 3 different techniques: Leadbetter-Politano, 3-stitch, and 2-stitch techniques. At our center, all renal transplant patients, including renal transplant recipients included in this study, were provided with a ureteral stent and a Foley catheter during transplant. In most cases, the ureteral stent was removed 10 days after surgery, which was followed by the withdrawal of the urinary catheter 24 hours later.
At our center, patients receiving renal allografts undergo renal ultrasonography both before and after transplant. In particular, ultrasonography after transplant was of interest and crucial importance. Ultrasonography, in addition to radiography and computed tomography without venous contrast medium, was also used to identify urinary calculi in patients presenting with symptoms of urolithiasis. Before transplant, renal ultrasonography was also conducted in the donor allograft.
Results
Incidence of urolithiasis in the renal graft
During our study period between January 2002 and December 2014, our analyses
showed 8 patients with urolithiasis in the renal graft, with 5 of these patients
presenting with urolithiasis who underwent the transplant procedure at the
Charité Campus Mitte. The other 3 underwent transplant at 2 other campuses of
the Charité University Hospital. Only those patients transplanted at Campus
Mitte were included in the incidence rate calculation, which was 0.45%
(calculated from a total of 1115 transplants conducted at our institution).
Patient characteristics
Table 1 presents patient demographic data, cause of end-stage renal disease,
relevant comorbidities, transplant source, transplant year, and time between
transplant and formation of stones. Five of the 8 patients were female, and mean
age of patients was 62 years (range of 41-76 y). One allograft came from a
living donor, whereas the other grafts were obtained from deceased donors. Two
patients underwent renal transplant twice. One of them died 8 years after
successful treatment of urolithiasis due to multiorgan dysfunction syndrome not
associated with renal stones. All grafts were stone free, as shown by both
pretransplant imaging of the allograft and in duplex ultrasonography after renal
transplant. Urinary stones formed a minimum of 2 months after transplant. Time
between transplant and diagnosis ranged between 2 and 98 months, with a mean of
21.5 months.
No complications occurred intraoperatively. Two rejections occurred, with 1 graft rejected 1 month before the detection of urinary calculi and the other graft rejected right after transplant. Both patients were treated without any problems affecting appropriate renal function.
Comorbidities predisposing urolithiasis
Almost all recipients had secondary hyperparathyroidism and 3 had
hyperuricemia. One patient had hypercalcemia due to parathyroid adenoma as a
predisposing comorbidity. After surgery, calcium levels normalized. However,
urinary stones were identified 2 months after surgery. There may have been a
causal connection between the occurrence of stones and the higher calcium level
in the blood. Nevertheless, a ureteral stone was identified and treated 1 year
later without recurrence of increased calcium levels in the blood. Half of the
patients had recurrent urinary tract infections, possibly predisposing urinary
stones.13 Two recipients had urosepsis a few months before the
diagnosis of urolithiasis, and another patient developed urosepsis in the
context of an occluded stone, suggesting an association between urosepsis and
the formation of stones. Calcifications in the native kidneys were found in 2
patients, one having secondary oxalosis and the other nephrocalcinosis as
primary diseases. Both had a history of urolithiasis before transplant.
Symptoms and clinical findings
Figure 1 depicts the symptoms and clinical findings at time of diagnosis or
recurrence of stones illustrating the percentage of each clinical finding. We
found that hydronephrosis and urinary tract infection were the leading symptoms
and clinical findings in our study patients, with other findings such as
elevated creatinine levels, hematuria, pain, and anuria also shown. Of
particular note was the occurrence of hydronephrosis in all patients except for
1 patient, in which the particular information could not be gathered. Urinary
tract infections were found in 5 patients, with all receiving treatment before
stone management. In most cases, urolithiasis was detected using diagnostic
imaging to clarify patient symptoms. In 2 patients, diagnosis was initially made
by chance with the use of imaging techniques. Neither of these patients had any
symptoms or clinical manifestations before diagnoses.
Stone characteristics
Table 2 shows stone characteristics, urolithiasis treatment, and follow-up
treatment. Initial diagnoses showed different numbers of stones, ranging from 1
to multiple, with all localized in the kidney and ureter. Five patients had
renal and 4 had ureteral stones. The minimum size of the initially identified
stone was 2 mm, and the maximum size was 21 mm. In 1 patient, a steinstrasse was
documented. Three patients were treated with ESWL, 4 with PNL, and 5 with
ureterorenoscopy. In addition, 1 patient, who first formed a stone in the
ureter, was treated with endoscopic lithotripsy for stone recurrence in the
bladder. This is the only patient who had stone formation outside the kidney and
ureter. One patient, who required special stone management, underwent a
pyelovesicostomy after 19 interventions.
Urolithiasis treatment in this series
Because of small stone size, the intervention for the first patient in the list
was ESWL. Because of residual calculi, a PNL was ultimately performed. The
second patient underwent ureterorenoscopy. Considering the formation of
steinstrasse, ESWL was excluded as treatment. In this patient, urosepsis evolved
1 month after ureterorenoscopy, presumably not in association with treatment.
In patient 4, a calculus located in the distal ureter was treated by
ureterorenoscopy. Patient 5, because of the large stone size and localization,
received PNL. Although patient 7 had small stones, the large number of stones
eventually made PNL a necessary treatment option. The last patient required PNL
because of the plurality and localization of the stones.
In 2 patients, complications after treatment were noted. In 1 patient, a hemorrhage was observed during PNL, requiring 3 treatments with packed red blood cells intraoperatively and postinterventional selective embolization of an artery in the lower pole of the kidney. The other complication occurred during placement of a ureteral stent, causing perforation and a partial tamponade that was managed by a mono-J stent. In both patients, normal kidney function and diuresis returned. No postoperative or postinterventional complications were documented.
Figure 2 illustrates interventions conducted, presenting ESWL as the most performed treatment, followed by ureterorenoscopy. However, because the patient with secondary oxalosis required 15 ESWLs and because the intervention frequency of 20 significantly diverged from that of the other patients, Figure 3 demonstrates the interventions in this series, excluding those used for the patient with secondary oxalosis. In contrast to Figure 2, Figure 3 indicates ureterorenoscopy as the most frequently used treatment, followed by PNL.
Not all interventions were performed one after another. One patient was under urologic surveillance for 2 years after ESWL. Because no spontaneous passage of renal stones was observed, this patient had 3 other interventions 2 years after the first intervention.
Case with secondary oxalosis
Three patients had recurrent urolithiasis (37.5%). Two had recurrent urinary
calculi just once after 24 and 16 months. In one case, namely, the patient with
secondary oxalosis, chronic urolithiasis in the transplant kidney was shown. At
follow-up, the 50-year-old patient, after undergoing 20 therapeutic procedures,
showed a stone-free transplant after pyelovesicostomy. However, secondary
oxalosis developed, most likely from Crohn disease, after 3 ileocecal resections
contributing to a short bowel syndrome and the formation of stones in his native
kidneys, which were treated with ureterorenoscopy and ESWL several times until
the patient required hemodialysis due to end-stage renal disease. The patient
received his first transplant in 2002. Two years later, after graft failure with
calcium oxalate accumulation, a second transplant procedure was conducted.
Eleven months after transplant, stones formed in his second graft, leading to
several interventions and procedures but without succeeding long-term stone
clearance. Urinary calculi recurred despite drinking 8 L of water per day and
low oxalate diet. Between December 2008 and April 2012, the patient received 7
ureteral stents. He had postrenal acute kidney injury 5 times during this
period, with 1 urosepsis because of an occluded stone, and had recurrent urinary
tract infections. Although recurrent urinary calculi were small, the patient
presented with hydronephrosis and elevated creatinine levels. Because of the
small stone size, he was initially treated with ESWL. Before 2010, the patient
received 8 ESWL treatments. In 2010, ESWL was conducted twice and then once in
2011. After formation of steinstrasse, ureterorenoscopy was performed twice in
2011. In 2012, the patient underwent 4 ESWL and 2 ureterorenoscopy procedures.
Finally, in the same year, the urolithiasis was treated with pyelovesicostomy
with Boari flap, without any complications or recurrence of stones at 32-month
follow-up after surgery. The patient’s creatinine level of 2.29 mg/dL indicated
a possibly slightly impaired graft function. However, compared with the
creatinine level before surgery, which was 3.4 mg/dL, and considering the
impending chronic graft failure before surgery, there clearly was an
improvement.
Outcomes
Creatinine levels ranged from 0.64 to 2.29 mg/dL, with a mean level of 1.27
mg/dL, excluding the patient who died due to multiorgan failure. The patient
with secondary oxalosis had impaired renal function, with creatinine levels
shown as 2.29 mg/dL. At follow-up, all patients were under urologic surveillance
and were stone free.
Discussion
The incidence rate of 0.45% in this study indicates that urolithiasis among kidney recipients is a rather uncommon urologic complication of the renal graft. Even when we included the 3 patients not transplanted at Campus Mitte, our incidence rate was still less than 1%. Urolithiasis appears to have a higher incidence in the general population. In Germany for example, the incidence of urolithiasis is 1.47%.15 One factor that might influence the occurrence of stones is daily liquid intake, which is supposed to be higher among kidney recipients than in the general population. Moreover, renal transplant recipients normally have a shorter ureter, which may facilitate faster passage of urinary stones. However, there are also conditions found in graft recipients that may lead to the development of stones. For example, immunosuppressive drugs are presumed to facilitate stone formation by way of influencing the metabolic profile.14
Although PNL is a promising procedure for rendering patients stone free after only 1 or 2 procedures, as confirmed in this and in other series,12,13,16 it was performed less frequently than ESWL and ureterorenoscopy. However, if we exclude the patient requiring 20 interventions, more invasive than noninvasive procedures were performed (78%), although stone size was rather small, with a maximum size of 21 mm. For management of stones smaller than 20 mm, Wong and associates14 suggested ESWL, whereas PNL was recommended for stones larger than 20 mm. In this study, the large number of stones and in 1 patient the occurrence of steinstrasse made invasive procedures favorable. Three patients required PNL as an invasive procedure for their multiple stones despite having small stones with a maximum size of 10 mm. Two of these patients underwent ESWL without success, resulting in later treatment with PNL. Krambeck and associates13 described 13 cases with urinary stones after kidney transplant treatment with PNL, effectuating stone-free allografts in 10 patients after only 1 intervention and in 3 other patients after the second one. In about one-fourth of these cases, postoperative complications were recorded, which is in contrast to this study, where no complications occurred postoperatively. However, 1 intraoperative PNL complication (a decrease in hemoglobin because of a hemorrhage, probably related to impaired wound healing) occurred in this series. Thus, both intra- and postoperative complications of PNL should not be neglected.
Interestingly, in contrast to other studies1,2 no urinary calculi were detected by diagnostic imaging during the perioperative period. Klingler and associates2 reported 4 cases in which caliceal stones were diagnosed both pre- and intraoperatively by ultrasonography and removed intraoperatively by pyelotomy. Five other patients with stones from donor grafts were noted postoperatively during ultrasonography and were treated conservatively, by surgery or by ESWL. One recipient who was treated conservatively developed an impaired graftfunction because of complications following urolithiasis. Thus, patients undergoing conservative therapy should be under attentive urologic surveillance.
Graft recipients having a history of urinary calculi should be given particular attention in view of a possible recurrence in the graft. In this series, 2 patients had urinary stones before transplant, in both cases causing end-stage renal disease. One of these patients underwent a pyelovesicostomy, rendering the patient stone free without recurrence of stones at 32-month follow-up. Pyelovesicostomy could be considered as an option for recurrent urinary stones in renal transplant patients. Flechner and associates17 performed autotransplant with pyelovesicostomy in 15 patients with recurrent metabolic stones, achieving a significant decrease in the number of further interventions. Salvatierra and associates18 reported 1 patient with short bowel syndrome and formation of calcium oxalate stones, similar to the patient with secondary oxalosis presented in this study. This patient, however, did not undergo renal allograft transplant and was rendered stone free after bilateral autotransplant with pyelovesicostomy. In review of the literature, however, we found no case of a reported pyelovesicostomy performed for the management of stones in the renal graft. Another possibility for treating a patient with secondary oxalosis due to a short bowel syndrome is intestinal transplant. Ceulemans and associates19 reported 2 cases of simultaneous kidney and intestinal transplant in patients with hyperoxaluria and urolithiasis evolving from short bowel syndrome after intestinal resection. One recipient developed urinary lithiasis after transplant, whereas the other was reported to be stone free since transplant. Both patients, unlike the patient with secondary oxalosis presented in this study, showed normal urinary oxalate excretion at follow-up. For these 2 patients, the primary cause for development of stones was Crohn disease, as presented also in our study, with increased excretion of urinary oxalate facilitating stone formation. This was resolved by intestinal transplant. This appears to be a rather favorable option for patients with short bowel syndrome. However, intestinal transplants have a higher risk of complications than other transplant procedures.19 Thus, a prudent and careful approach in terms of intestinal transplant is recommended.
In general, treatment of urolithiasis in renal allograft patients does not notably differ from that for the general population. However, in cases with multiple small calculi, more invasive procedures like PNL and ureterorenoscopy seem more advisable than ESWL. Conservative procedures should be conducted carefully to prevent complications and graft impairment in the patient’s solely functioning kidney. Pyelovesicostomy can be considered as an alternative procedure for patients with recurrent and intractable urinary stones, especially when severe graft impairment or even failure is feared.
Limitations and Conclusions
This was a retrospective analysis, making it difficult to establish a reliable therapy sequence for urolithiasis in renal grafts. Considering the small patient cohort and the absence of larger studies, more research is warranted. Moreover, pyelovesicostomy has been rarely conducted as a therapeutic intervention in renal transplant recipients and should be performed in exceptional cases with recurrent urinary stones.
References:
- Ferreira Cassini M, Cologna AJ, Ferreira Andrade M, et al. Lithiasis in
1,313 kidney transplants: incidence, diagnosis, and management. Transplant
Proc. 2012;44(8):2373-2375.
CrossRef - PubMed - Klingler HC, Kramer G, Lodde M, Marberger M. Urolithiasis in allograft
kidneys. Urology. 2002;59(3):344-348.
CrossRef - PubMed - Poullain J, Devevey JM, Mousson C, Michel F. [Management of lithiasis of
kidney transplant]. Prog Urol. 2010;20(2):138-143.
CrossRef - PubMed - Shoskes DA, Hanbury D, Cranston D, Morris PJ. Urological complications
in 1,000 consecutive renal transplant recipients. J Urol. 1995;153(1):18-21.
CrossRef - PubMed - Hayes JM, Streem SB, Graneto D, Hodge EE, Steinmuller DR, Novick AC.
Renal transplant calculi. A reevaluation of risks and management.
Transplantation. 1989;47(6):949-952.
CrossRef - PubMed - Benoit G, Blanchet P, Eschwege P, Jardin A, Charpentier B. Occurrence
and treatment of kidney graft lithiasis in a series of 1500 patients. Clin
Transplant. 1996;10(2):176-180.
PubMed - Cho DK, Zackson DA, Cheigh J, Stubenbord WT, Stenzel KH. Urinary calculi
in renal transplant recipients. Transplantation. 1988;45(5):899-902.
CrossRef - PubMed - Mamarelis G, Vernadakis S, Moris D, et al. Lithiasis of the renal
allograft, a rare urological complication following renal transplantation: a
single-center experience of 2,045 renal transplantations. Transplant Proc.
2014;46(9):3203-3205.
CrossRef - PubMed - Stravodimos KG, Adamis S, Tyritzis S, Georgios Z, Constantinides CA.
Renal transplant lithiasis: analysis of our series and review of the
literature. J Endourol. 2012;26(1):38-44.
CrossRef - PubMed - Karam G, Kälble T, Alcaraz A, et al. Guidelines on Renal Transplantation. European Association of Urology; 2014:76-77. http://uroweb.org/wp-content/uploads/27-Renal-Transplant_LRV2-May-13th-2014.pdf. Accessed December 17, 2015.
- Rhee BK, Bretan PN, Jr., Stoller ML. Urolithiasis in renal and combined
pancreas/renal transplant recipients. J Urol. 1999;161(5):1458-1462.
CrossRef - PubMed - Lu HF, Shekarriz B, Stoller ML. Donor-gifted allograft urolithiasis:
early percutaneous management. Urology. 2002;59(1):25-27.
CrossRef - PubMed - Krambeck AE, Leroy AJ, Patterson DE, Gettman MT. Percutaneous
nephrolithotomy success in the transplant kidney. J Urol.
2008;180(6):2545-2549.
CrossRef - PubMed - Wong KA, Olsburgh J. Management of stones in renal transplant. Curr Opin
Urol. 2013;23(2):175-179.
CrossRef - PubMed - Hesse A, Brandle E, Wilbert D, Kohrmann KU, Alken P. Study on the
prevalence and incidence of urolithiasis in Germany comparing the years 1979
vs. 2000. Eur Urol. 2003;44(6):709-713.
CrossRef - PubMed - Rifaioglu MM, Berger AD, Pengune W, Stoller ML. Percutaneous management
of stones in transplanted kidneys. Urology. 2008;72(3):508-512.
CrossRef - PubMed - Flechner SM, Noble M, Tiong HY, Coffman KL, Wee A. Renal
autotransplantation and modified pyelovesicostomy for intractable metabolic
stone disease. J Urol. 2011;186(5):1910-1915.
CrossRef - PubMed - Salvatierra O, Jr, Longaker M, Crombleholme T. Bilateral renal
autotransplantation with pyelovesicostomy: a surgical treatment of
refractory enteric hyperoxaluria. Surgery. 1989;105(3):430-435.
PubMed - Ceulemans LJ, Nijs Y, Nuytens F, et al. Combined kidney and intestinal
transplantation in patients with enteric hyperoxaluria secondary to short
bowel syndrome. Am J Transplant. 2013;13(7):1910-1914.
CrossRef - PubMed

Volume : 15
Issue : 2
Pages : 164 - 170
DOI : 10.6002/ect.2016.0040
From the Department of Urology, Charité University Hospital, Berlin, Germany
Acknowledgements: The authors declare that they have no sources of
funding for this study, and they have no conflicts of interest to declare.
Corresponding author: Frank Friedersdorff, Charitéplatz 1, 10117 Berlin,
Germany
Phone: +49 30 450 615 219
E-mail:
frank.friedersdorff@charite.de
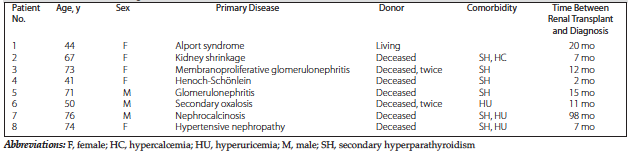
Table 1. Patient and Renal Allograft Data
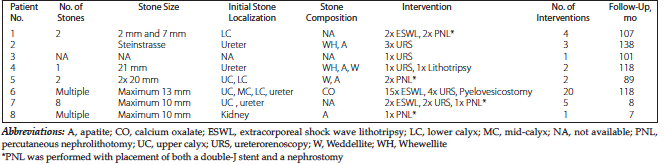
Table 2. Stone Characteristics and Treatment
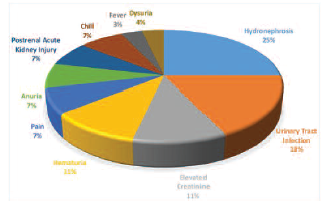
Figure 1. Patient Symptoms and Clinical Findings
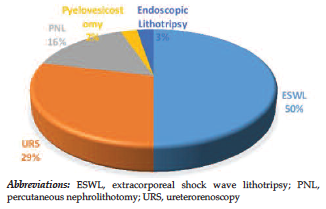
Figure 2. Urolithiasis Treatment in All Study Patients
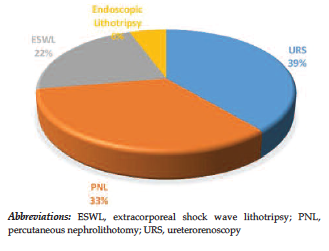
Figure 3. Treatment of Urolithiasis Without Presence of Secondary Oxalosis